Drugs, Health Technologies, Health Systems
Reimbursement Recommendation
Inebilizumab (Uplizna)
Indication: Adults with immunoglobulin G4-related disease
Sponsor: Amgen Canada Inc.
Final recommendation: Reimburse with conditions
Summary
What Is the Reimbursement Recommendation for Uplizna?
Canada’s Drug Agency (CDA-AMC) recommends that Uplizna be reimbursed by public drug plans for immunoglobulin G4-related disease (IgG4-RD) if certain conditions are met.
Why Did CDA-AMC Recommend Reimbursement?
The Canadian Drug Expert Committee (CDEC) determined that Uplizna demonstrates acceptable clinical value versus placebo in patients with IgG4-RD. However, CDEC concluded that it is uncertain whether inebilizumab demonstrates acceptable clinical value when compared with appropriate comparators (i.e., off-label rituximab, a B-cell depleting drug currently used in clinical practice in patients with IgG4-RD). Given that inebilizumab is expected to be an alternative treatment to rituximab, comparable clinical value to rituximab was considered to represent acceptable clinical value.
Evidence from a clinical trial showed that patients who received Uplizna for 12 months experienced fewer flares requiring treatment and their condition required lower doses of glucocorticoids compared with placebo. In addition, more patients who received Uplizna experienced complete remission. Therefore, inebilizumab may address patient-identified unmet needs for treatments with meaningful impact on disease control, especially glucocorticoid-free maintenance of remission. Results from the trial about health-related quality of life (HRQoL) were inconclusive due to substantial uncertainty caused by a lack of tools validated in this population. Patients who received Uplizna were at higher risk of infections and of having too few blood cells circulating in their blood, which are common side effects of this class of drugs due to their immunosuppressive effect. Clinical expert input suggested that harms were considered manageable in clinical practice, and overall, Uplizna was considered to have an acceptable safety profile. The clinical trial enrolled a small number of patients, but CDEC acknowledged that it is difficult to generate evidence for drugs used in the treatment of rare diseases.
There is a lack of information to compare the efficacy and safety of Uplizna with other drugs that are currently used in clinical practice to treat patients with IgG4-RD, even if they have been approved by Health Canada for use in other conditions. However, CDEC established that there was significant unmet clinical need due to the rarity and severity of IgG4-RD. The committee concluded that Uplizna may address a significant unmet clinical need to a degree that justifies a positive recommendation despite the uncertainty in the clinical value.
Which Patients Are Eligible for Coverage?
Uplizna should only be reimbursed for adult patients with a confirmed clinical diagnosis of IgG4-RD who have an active or recent flare.
What Are the Conditions for Reimbursement?
Uplizna should only be reimbursed if patients meet the conditions detailed in Table 1, and if the cost of Uplizna is reduced. Initiation and management of therapy with Uplizna should be managed by a specialist with expertise in treating IgG4-RD. The recommended period for initial reimbursement is 6 months, followed by annual renewals thereafter. Renewal is recommended to be based on an observation of clinical benefit as assessed by the treating physician. Uplizna should be discontinued if the treating physician determines that the treatment is no longer providing adequate benefit or if more than 20 mg/day of prednisone (or equivalent) is required on an ongoing basis to prevent disease flares after the initial flare treatment and steroid taper have been completed.
Review Background
Disease background: IgG4-RD is a rare, complex, immune-mediated fibroinflammatory disease with periods of disease relapse – or flares – and remission. It was formally recognized as a disease in 2003. There are no global or Canada-specific estimates of its prevalence; in the US, as of 2019, the point prevalence was estimated to be 5.3 per 100,000 persons. IgG4-RD can affect any organ system, may occur in multiple organs at once, and the affected locations may vary over a patient’s lifetime. Commonly affected organs include the pancreas, kidneys, eyes, salivary glands, and retroperitoneum. Signs and symptoms are therefore highly variable and may include tumour-like inflammatory masses, tissue fibrosis, organ enlargement, and a wide range of symptoms related to organ-specific dysfunction. Each relapse causes organ and tissue damage that may be irreversible and cumulative; ultimately, IgG4-RD may result in life-threatening, end-stage organ damage. The onset of disease is typically slow and cryptic, and diagnosis often occurs after irreversible organ damage has already taken place.
Indication and reimbursement request: Inebilizumab (Uplizna) has been approved by Health Canada for adults with IgG4-RD to reduce the frequency of flares. The sponsor is seeking reimbursement for this patient population.
Drug under review: Inebilizumab is a B-cell depleting therapy (anti-CD19+). It is available as single-dose vials containing 100 mg inebilizumab in 10 mL solution (10 mg/mL) for IV infusion to be administered once every 6 months, with an additional dose required 2 weeks after the first dose.
Treatment costs: At the submitted price of $25,623.00 per 10 mL vial, the annual cost of inebilizumab is expected to be $230,607.00 per patient in the first year of treatment, and $153,738.00 per patient in subsequent years, based on the Health Canada–recommended dosage.
Highlights of Input From Interested Parties
The 4 patient groups (Vasculitis Foundation Canada and the Colorectal Cancer Resource & Action Network; Arthritis Consumer Experts; The Sumaira Foundation; and the Canadian Organization for Rare Disorders) noted the following regarding impacts of the disease, unmet needs, and important outcomes:
IgG4-RD affects the ability to work and/or perform normal activities of daily and family life, relationships, independence, confidence, mental health, and emotional well-being. During flares, patients described severe fatigue, joint pain, muscle pain, abdominal pain, brain fog, trouble finding words, and loss of stamina. Symptoms were often unpredictable and disabling. Over time, patients experience functional loss, persistent uncertainty, and anxiety related to the risk of disease relapse and silent organ damage.
Patients living with IgG4-RD typically experience high cumulative exposure to corticosteroids and may be dependent on corticosteroids to control disease flares and prevent additional organ damage. High exposure to corticosteroids is associated with increasing intolerance, side effects, and downstream steroid-related health risks.
There are no other therapies indicated for the treatment of IgG4-RD, and all therapies used in current clinical practice are done so off label. The input noted that the most effective and safe drug, based on real-world experience, is rituximab, which is inconsistently reimbursed or simply inaccessible across Canada.
Patients have an unmet need for an effective and tolerable drug that can help them achieve their treatment goals, including resolving the current flare, preventing or reducing the incidence of future flares, and thereby reducing the downstream, cumulative organ damage caused by flares that may result in organ dysfunction or failure. Reducing exposure to and dependency on corticosteroids is noted as another high-priority treatment goal.
The 3 clinician groups (the Canadian Rheumatology Association; the Autoimmune and Rare Liver Disease Programme, Toronto General Hospital; and CanVasc and Canadian MD colleagues with interest in IgG4-RD) and the clinical experts consulted by CDA-AMC noted the following regarding unmet needs arising from the disease and place in therapy for the drug under review:
Inebilizumab is the first drug indicated for the treatment of IgG4-RD in Canada. Lack of reimbursement for B-cell depleting therapy such as rituximab (off label; anti-CD20+) or inebilizumab (anti-CD19+) is noted as a critical barrier to appropriate treatment in IgG4-RD. Access to B-cell depleting therapies is expected to address the broadly unacceptable level of exposure to corticosteroids in patients living with IgG4-RD.
B-cell depleting therapies are relevant for both induction and maintenance, with or without concurrent corticosteroids during the induction phase. In the absence of evidence supporting appropriate treatment sequencing, the clinician input suggested that both inebilizumab and rituximab should be available as first-line therapy for adult patients with IgG4-RD who have at least 1 critical affected organ or site, multiple affected organs or sites, or threat to organ or life as a result of IgG4-RD.
The participating public drug programs provided input regarding considerations for initiation, renewal, discontinuation, and prescribing of therapy; health system implementation considerations; relevant comparators; and system and economic considerations.

Note: The perspectives shared by people with lived experience who present to the committee reflect their individual experiences and are not necessarily representative of all people with the same condition or course of treatment. Their insights provide valuable context about what a patient, support person, or caregiver might go through with this condition or treatment, helping to inform the committee’s deliberations. These narratives complement other forms of evidence and input and should be considered as 1 element contributing to a broader understanding of the condition and treatment under review.
Recommendation
With a vote of 15 in favour to 1 against, CDEC recommends that inebilizumab be reimbursed for IgG4-RD only if the conditions listed in Table 1 are met.
Table 1: Reimbursement Conditions and Reasons
Reimbursement condition | Reason | Implementation guidance |
|---|---|---|
Initiation | ||
| Evidence from the MITIGATE study demonstrated that treatment with inebilizumab resulted in added clinical benefits in adult patients with IgG4-RD who had a recent or active flare that was affecting at least 2 organs or sites. Eligible patients in the MITIGATE trial were required to fulfill the 2019 ACR-EULAR classification criteria for IgG4-RD. Expert input suggests that implementation of these criteria in clinical practice may not be feasible due to the increased health care system burden. | Condition 1.2: Diagnosis of IgG4-RD is complex and is based on numerous clinical, serological, radiologic, and pathologic evaluations. Diagnosis cannot be made based on elevated serum IgG4 alone due to insufficient specificity and sensitivity. Numerous medical assessments may be required to rule out conditions with similar presentations. Biopsy-proven IgG4-RD is definitively diagnosed; however, CDEC notes that not all sites can be safely biopsied. Because IgG4-RD is a rare and relatively newly recognized disease, practices around diagnosis and treatment are likely to evolve; at this time, CDEC recognizes that organ-specific criteria might not exist for all possible manifestations of IgG4-RD. Condition 1.3: CDEC noted that there is no standard time frame definition for a recent flare. In clinical practice, a recent flare typically refers to a flare within the prior 6 months. Condition 1.3: A critical site refers to an organ, organ function, or the patient’s life being threatened by the disease; for example, a critical organ or site in which disease involvement places the patient at risk of significant dysfunction, irreversible damage, or life-threatening complications. Based on clinical expert input, CDEC noted the high need for a B-cell depleting treatment in patients with any of the following: visceral organ involvement; critical organ systems affected; symptomatic patient with multiple organ systems affected; multiple prior disease relapses; progressive fibrotic or otherwise irreversible organ damage; reduced organ function; threat to organ or life; or high risk of disease relapse based on disease presentation and history. The evidence from the MITIGATE study is expected to be generalizable to these patient populations. Dependency on corticosteroids refers to the use of more than 5 mg/day of prednisone equivalent for the continued long-term maintenance – not induction – where patients cannot taper corticosteroids without having a flare. In the context of IgG4-RD, the term flare is interchangeable with disease relapse, exacerbation, attack, and other similar vocabulary that might be used and vary across clinicians and/or jurisdictions. |
2. Duration of initial authorization is 6 months. | Assessment of response at 6 months, after administration of the third dose of inebilizumab, is consistent with clinical practice in Canada based on expert input. The MITIGATE trial assessed the primary and secondary end points at 52 weeks during the randomized controlled phase. | CDEC recognized that access to appropriate prescribers may be limited in some jurisdictions, and delays in assessment may exceed the initial authorization timeline. Therefore, public drug plans may consider extending the initial authorization period (e.g., up to 12 months) to accommodate these constraints and ensure equitable access. |
Renewal | ||
3. For renewal after initial authorization, the physician must provide proof of clinical response to inebilizumab as assessed by the treating physician. | The renewal condition ensures that inebilizumab is reimbursed in patients benefiting from the therapy. | CDEC noted based on clinical expert input that defining universally applicable criteria for treatment response in IgG4-RD is not feasible given the heterogeneity of disease presentation. Any given patient may have a different set of organ systems affected, with markedly different clinical signs and symptoms, health impacts, and radiologic findings. Assessment of response conducted by a specialist in clinical practice may be documented based on clinical, radiological, and serologic improvements. For example, proof of clinical response may include improvement or stabilization in disease activity, organ function, imaging or serologic findings, reduction in flare frequency or severity, reduction in corticosteroid requirements, and meaningful patient-reported improvement in symptoms, functioning, or ability to participate in daily life. |
4. Assessment of treatment response for renewal after initial authorization and subsequent renewals may be conducted annually. | The MITIGATE trial assessed the primary and secondary end points at 52 weeks during the randomized controlled phase. | — |
Discontinuation | ||
5. Inebilizumab should be discontinued if any of the following occur: 5.1. loss of clinical response to treatment as assessed by the treating physician 5.2. maintenance regimen requiring more than 20 mg/day of prednisone equivalent to prevent a flare during treatment with inebilizumab (excluding the initial induction and taper for treatment of the active flare). | These signal lack of adequate response to inebilizumab based on clinician input. | Condition 5.2: Input from clinical experts and clinician groups noted that discontinuation would be considered in clinical practice when patients experience objective progression or disease relapse while being treated with inebilizumab, which was defined as requiring concurrent steroid therapy of greater than 20 mg/day of prednisone or equivalent for continued, long-term maintenance prevention of flares, besides the initial induction and taper. Based on clinical expert input, CDEC noted that patients who elect to discontinue inebilizumab as a result of being in sustained remission should be allowed to reinitiate inebilizumab in the event of a flare occurring after treatment discontinuation. CDEC noted that an observed loss of clinical response, when assessed based on 1 specific organ or site that has been affected by recurrent flares, may be due to accumulated irreversible fibrotic damage to the affected organ, and not necessarily because inebilizumab was ineffective for the patient’s IgG4-RD. In such cases, public drug plans may consider reinitiating inebilizumab or another B-cell depleting therapy in the case of a subsequent flare affecting a different organ or site. |
Prescribing | ||
6. Inebilizumab should be prescribed by clinicians with expertise in the diagnosis and management of IgG4-RD. | IgG4-RD is a rare and complex disease. Accurate diagnosis and management of patients with IgG4-RD is important to ensure that inebilizumab is prescribed for appropriate patients and that adverse effects are managed in a timely manner. | Because IgG4-RD can affect nearly any organ system, CDEC noted that patients may present to nearly any specialty with management needs related to organ-specific dysfunction. Therefore, CDEC did not restrict the specialists who may prescribe treatment with inebilizumab, but reiterates that prescribers need to have experience in the diagnosis and management of patients with IgG4-RD. In rural and remote areas, or in other circumstances where patients have a barrier to accessing a specialist, ongoing care could be managed by other clinicians, in consultation with the prescribing specialist. |
7. Inebilizumab can be used with or without concurrent corticosteroids for induction and/or maintenance. | The MITIGATE study included a mandatory corticosteroid taper that initiated at the same time as inebilizumab for maintenance. | Based on clinical expert input, CDEC noted that not all patients receiving inebilizumab will require concurrent corticosteroid treatment for induction. CDEC noted that if concurrent corticosteroid treatment was used for maintenance, the dose of prednisone should not exceed 20 mg/day. |
8. Inebilizumab should not be used in combination with other B-cell depleting therapies, such as rituximab. | There is no evidence to support combination therapy with multiple B-cell depleting drugs in IgG4-RD. | — |
Pricing | ||
9. A reduction in price. | Using CDA-AMC scenario analysis 2, the ICER for inebilizumab plus BSC was $2,585,721 per QALY gained when compared with BSC in the indicated population. A band 4 price reductiona would be required to achieve cost-effectiveness at a $50,000 and $100,000 per QALY threshold. Price reductions for any given willingness-to-pay threshold are available in the CDA-AMC Main Report and Supplemental Material document. The cost-effectiveness of inebilizumab plus BSC versus BSC alone is highly uncertain due to limitations in the structure of the sponsor’s pharmacoeconomic model, its representation of current clinical practice in Canada (particularly for subsequent therapies), and the availability of long-term evidence. The cost-effectiveness relative to other B-cell depleting treatments (e.g., rituximab) used off label in the indicated population is unknown given the lack of evidence regarding comparative efficacy for the indicated population. To ensure cost-effectiveness, inebilizumab should also be negotiated so that the drug price does not exceed the least costly B-cell depleting treatment reimbursed for the indicated population. | The CDA-AMC analysis is based on public list prices for all treatments. Further price reductions may be required if there are price arrangements (discounts) currently in place for any treatment included in the economic analysis. Likewise, further price reductions may be required to address economic feasibility of adoption. |
Feasibility of adoption | ||
10. The economic feasibility of adoption of inebilizumab must be addressed. | At the submitted price, the incremental budget impact of inebilizumab is expected to be greater than $40 million in years 2 and 3. At the submitted price, the magnitude of uncertainty in the budget impact must be addressed to ensure the feasibility of adoption, given the difference between the sponsor’s estimate and the CDA-AMC estimate(s). | — |
ACR = American College of Rheumatology; BSC = best supportive care; CDA-AMC = Canada’s Drug Agency; CDEC = Canadian Drug Expert Committee; EULAR = European League Against Rheumatism; ICER = incremental cost-effectiveness ratio; IgG4-RD = immunoglobulin G4 related disease; QALY = quality-adjusted life-year.
aFor the statement regarding the size of the price reduction required, band 1 = 1% to 24%, band 2 = 25% to 49%, band 3 = 50% to 74%, and band 4 = 75% or greater.
Rationale for the Recommendation
Clinical Value
Based on the totality of the available clinical evidence, CDEC concluded that inebilizumab demonstrates acceptable clinical value versus placebo in patients with IgG4-RD to reduce the frequency of flares. However, CDEC concluded that it is uncertain whether inebilizumab demonstrates acceptable clinical value when compared with appropriate comparators (i.e., off-label rituximab, a B-cell depleting drug currently used in clinical practice in patients with IgG4-RD). Given that inebilizumab is expected to be an alternative treatment to rituximab, comparable clinical value to rituximab was considered to represent acceptable clinical value.
Evidence from 1 phase III, double-blind, placebo-controlled trial (the MITIGATE trial; N = 135) showed that inebilizumab resulted in a clinically important reduction in treated disease flares after 52 weeks of treatment compared with placebo. More patients who received inebilizumab met the criteria for flare-free, glucocorticoid-free complete remission at 52 weeks; in line with those findings, inebilizumab also reduced the dose of glucocorticoids used to treat disease flares during the study. Therefore, inebilizumab may address patient-identified unmet needs for treatments with meaningful impact on disease control, especially glucocorticoid-free maintenance of remission. However, inebilizumab may have little to no impact on patients’ HRQoL and the common symptom of fatigue compared to placebo; there was substantial uncertainty in these findings due to imprecision and lack of disease-specific HRQoL metrics for IgG4-RD. Although the sample size of the MITIGATE trial was small, CDEC acknowledges the feasibility challenges in generating evidence for drugs used in the treatment of rare diseases. Evidence from the associated long-term extension (LTE) study was supportive of sustained clinical benefit on disease flare despite the inherent limitations of the study design; however, the LTE did not inform on HRQoL in the longer term.
With regards to safety, evidence from the MITIGATE trial showed that inebilizumab may increase the incidence of serious adverse events (SAEs) compared to placebo. Inebilizumab was also associated with an increased risk of infections, including opportunistic and serious infections, given the immunosuppressive nature of the drug. Cytopenia was also more common in patients receiving inebilizumab. Clinical expert input suggested that harms were considered manageable in clinical practice, and consistent with the known toxicities of B-cell depleting therapies. LTE findings suggested a consistent harms profile during extended follow-up; the study was however small and unlikely to detect uncommon side effects. Overall, inebilizumab was considered to have an acceptable and tolerable safety profile.
There is a lack of data on the comparative efficacy and safety of inebilizumab versus off-label comparators; of these, rituximab is of particular interest due to its mechanism of action through B-cell depletion. Based on clinical expert input, which was informed by experience from clinical practice and observational evidence, CDEC noted that clinicians consider rituximab as a disease-specific, effective therapy – especially in terms of durability of remission – with limited toxicity compared to other drugs currently available for the treatment of IgG4-RD. However, patients with IgG4-RD do not consistently have access to off-label rituximab for the treatment of IgG4-RD, except on an exceptional case-by-case basis. CDEC acknowledged the patient and clinician input highlighting the current lack of access to B-cell depleting therapies as an important barrier to appropriate treatment.
CDEC concluded that inebilizumab demonstrates added clinical benefit compared with placebo; however, uncertainty remained regarding its comparative clinical value versus rituximab and other off-label therapies used in clinical practice. Therefore, CDEC was unable to conclude on reimbursement based on clinical value alone.
Further information on the committee’s discussion around clinical value is provided in the Summary of Deliberation section.
Considering Significant Unmet Clinical Need
CDEC established that there was significant unmet clinical need due to the rarity and severity of IgG4-RD. Patients and clinicians highlighted a significant need for safe and tolerable therapies that can meaningfully reduce the number and severity of disease flares; prevent cumulative irreversible organ damage and the potential for downstream organ failure or death; and reduce the need for high exposure to corticosteroids to manage IgG4-RD.
CDEC concluded that treatment with inebilizumab may address a significant unmet clinical need to a degree that justifies a positive recommendation despite the uncertainty in the clinical value.
Further information on the committee’s discussion around unmet clinical need is provided in the Summary of Deliberation section.
Developing the Recommendation
Due to the uncertainty in clinical value, CDEC could not recommend whether to reimburse inebilizumab or not based on clinical value alone. Therefore, the committee also considered whether inebilizumab addresses a significant unmet clinical need. CDEC concluded that inebilizumab addresses a significant unmet clinical need with an acceptable level of certainty. Based on the preceding considerations, CDEC recommended that inebilizumab be reimbursed. As part of the deliberation on whether to recommend reimbursement or not, the committee also considered unmet nonclinical need and health inequity. Information on this discussion is provided in the Distinct Social and Ethical Considerations domain in the Summary of Deliberation section.
Because CDEC recommended that inebilizumab be reimbursed, the committee also deliberated on whether reimbursement conditions should be added to address important economic considerations, health system impacts, or social and ethical considerations, or to ensure clinical value is realized. The resulting reimbursement conditions, with accompanying reasons and implementation guidance, are stated in Table 1.
Summary of Deliberation
CDEC considered all domains of value of the deliberative framework before developing its recommendation: clinical value, unmet clinical need, distinct social and ethical considerations, economic considerations, and impacts on health systems. For further information on the domains of value, refer to Expert Committee Deliberation at Canada’s Drug Agency.
The committee considered the following key discussion points, organized by the 5 domains of value.
Clinical Value
Appropriate comparators: Treatments currently used in clinical practice in Canada for the treatment of IgG4-RD are used off label and include rituximab, azathioprine, mycophenolate mofetil, methotrexate, and low-dose corticosteroids (e.g., prednisone). Of these, CDEC noted that off-label rituximab is of particular relevance, as both inebilizumab and rituximab share a similar mechanism of action in the treatment of IgG4-RD, through B-cell depletion. Based on clinical expert input, which was informed by experience from clinical practice and observational evidence, CDEC noted that clinicians consider rituximab as a disease-specific, effective therapy – especially in terms of durability of remission – with limited toxicity compared to other drugs currently available for the treatment of IgG4-RD.
Place in therapy: CDEC noted that, based on clinical expert input, inebilizumab is expected to occupy a similar place in therapy to rituximab as a B-cell depleting treatment option for patients with IgG4-RD. However, CDEC acknowledged that rituximab as maintenance therapy for patients with IgG4-RD is not consistently reimbursed by all jurisdictions and, therefore, access to rituximab might not be equitable for all patients across Canada who are covered by a publicly funded drug plan. Based on clinical expert input, CDEC acknowledged that it would be ideal if all patients across Canada had equitable access to rituximab for IgG4-RD.
Efficacy and safety versus placebo: Evidence from 1 phase III randomized controlled study (MITIGATE; N = 135) demonstrated that inebilizumab results in a clinically important improvement in the following outcomes: a reduction in the risk of first disease flare requiring treatment (hazard ratio for median days to first treated disease flare = 0.13; 95% confidence interval [CI], 0.06 to 0.28; a reduction in the annualized rate of flares [61 fewer flares per 100 patients per year, 95% CI, 82 to 39 fewer]); an increase in the proportion of patients achieving flare-free, glucocorticoid-free complete remission (36.5% greater; 95% CI, 21.1% to 51.9%); and a lower least squares mean total glucocorticoid use per patient (−1,264.2 mg prednisone equivalent; 95% CI, −1,689.2 to −839.2 mg). Regarding HRQoL, there were no clinically important differences observed between treatment groups based on the Short Form (36) Health Survey physical or mental component scores, nor on the FACIT-Fatigue scale. However, the metrics used in the MITIGATE trial were not validated in patients with IgG4-RD and it is uncertain whether they are sufficiently responsive to reflect meaningful improvements in this condition. Inebilizumab was associated with a higher proportion of patients experiencing adverse events or SAEs related to infections and infestations, including opportunistic infections. Compared to placebo, inebilizumab was associated with a higher proportion of patients experiencing SAEs in general, and adverse events of special interest such as cytopenia. No new safety signals were identified in the MITIGATE study or in the interim data from the open-label extension study.
Clinical importance of treatment effects versus placebo: CDEC concluded that the benefits of inebilizumab in reducing the frequency and severity of flares and glucocorticoid exposure were clinically meaningful compared to placebo based on clinical expert input. CDEC noted that these end points reflect the unmet needs expressed by patient and clinician group inputs. The committee was unable to conclude that inebilizumab has any meaningful benefit on the HRQoL end points that were assessed in the MITIGATE trial.
Certainty of the evidence versus placebo: The certainty of the evidence versus placebo was high for the objective end points related to flares and glucocorticoid exposure, which were controlled for multiplicity. The certainty of the evidence was low for patient-reported end points and HRQoL, because these metrics have not been validated in populations with IgG4-RD and it is unknown whether they are valid and sufficiently sensitive to detect clinically important differences in this population. The certainty of the evidence was also low for SAEs due to imprecision.
Long-term safety and efficacy: An ongoing, phase III, multicentre, open-label extension of the MITIGATE study was reviewed as supportive evidence. Interim results did not reveal any additional safety concerns and are supportive of durability of treatment effect. However, the ability to draw conclusions was limited by a few patients, interim data, and the lack of a comparator group.
Efficacy versus off-label active comparators: There is no evidence to properly assess the comparative efficacy and safety of inebilizumab versus off-label maintenance drugs, including rituximab, azathioprine, mycophenolate mofetil, methotrexate, and low-dose prednisone. These are clinically relevant, but there is a lack of high-quality evidence supporting their use in IgG4-RD, which makes conducting robust indirect comparisons not realistically feasible.
Assessment of treatment effect: The IgG4-RD responder index was used in the MITIGATE trial to define lack of evident disease activity as part of the key secondary end point of remission; lack of evident disease activity could also be determined by the investigator at week 52. It is a validated clinical instrument for longitudinal assessment of IgG4-RD disease activity, designed for structured assessment of treatment response by clinical investigators. Based on clinical expert input, CDEC noted that the IgG4-RD responder index is not used in clinical practice. Input suggests that the tool could be integrated for assessment of treatment response as long as clinicians have proper training and a thorough understanding of the clinical breadth of IgG4-RD. However, the minimum threshold for defining an acceptable clinical response to treatment is unknown. CDEC also noted that there is no defined threshold for what may constitute a significant worsening on the IgG4-RD responder index.
Clinical value: Based on all of the preceding considerations, the committee determined there was added clinical value associated with inebilizumab versus placebo in the treatment of IgG4-RD. It is unknown whether there is added clinical value associated with inebilizumab versus active comparators used off label in Canada; however, there are numerous barriers to accessing these off-label treatments and no robust evidence to support their use in IgG4-RD.
Unmet Clinical Need
Input on unmet clinical need: Patients with IgG4-RD and their caregivers identified a need for safe and tolerable treatments that can effectively reduce or eliminate IgG4-RD disease flares as well as their cumulative exposure to corticosteroids, which are associated with poor tolerability and downstream risks and side effects, especially at the high cumulative exposure that is often seen in the management of IgG4-RD flares. Reduction or elimination of disease flares is also expected to reduce downstream irreversible organ damage, especially in patients whose manifestations are organ threatening or life threatening.
Severity of the disease: The committee recognized clinical expert input, as well as patient and clinician group inputs, that IgG4-RD is a chronic, incurable condition that is highly heterogeneous and can change significantly over a patient’s lifetime. Depending on the affected organs or organ systems and the severity of the disease in each individual, patients may have mild to severe, and even life-threatening disease. IgG4-RD is associated with an elevated risk of mortality; cumulative fibrotic damage can irreversibly damage organ function or cause total loss of organ function, which may be severely disabling or fatal depending on the nature of the organ. Additionally, on-demand treatment of flares relies on corticosteroids, which have a high side-effect burden and downstream risks given high cumulative exposure.
Availability of treatment options and barriers to reimbursement: Although several off-label therapies have been used to treat IgG4-RD in clinical practice, none are currently indicated for the treatment of IgG4-RD in Canada. There is no robust evidence to support their use, and reimbursement access for these therapies in patients with IgG4-RD is inconsistent. In particular, input from clinical experts and from patient and clinician groups noted that lack of reimbursement access to rituximab – another B-cell depleting therapy – is a critical barrier to appropriate treatment for patients with IgG4-RD in Canada. CDEC acknowledged from the input received that rituximab may be reimbursed in some provinces only on an exceptional case-by-case basis for the management of IgG4-RD and noted that inequitable access to rituximab across jurisdictions was identified by clinicians and patients as an important barrier to optimal management of IgG4-RD. Based on experience from clinical practice and observational evidence, clinicians noted that conventional immunosuppressants are effective treatment options; however, for patients with recurrent flares or critical organ involvement, and for those whose disease is treatment refractory, clinicians consider B-cell therapies as a first-line, effective treatment option for IgG4-RD, with limited toxicity.
Significant unmet clinical need: Due to challenges with evidence generation associated with the rarity of IgG4-RD, the severity of the disease despite the currently available treatment options, and the lack of access to effective and safe treatment options, CDEC considered there to be significant unmet need as described in the recommendation framework in the Procedures for Reimbursement Reviews. CDEC concluded that treatment with inebilizumab may address the significant unmet clinical need to a degree that justifies a positive recommendation despite the uncertainty in the clinical value.
Distinct Social and Ethical Considerations
Input on unmet nonclinical need: CDEC noted several unmet nonclinical needs, including treatment burden due to the rarity of the disease. CDEC acknowledged that patients with IgG4-RD face multiple types of treatment burden, and their HRQoL may be significantly compromised. As such, patients and caregivers highlighted the substantial and various burdens that come with the condition in the input received by CDA-AMC. The input specifically noted the burden of the diagnostic journey, managing and coordinating numerous specialists, a high amount of personal research and self-advocacy needed to get appropriate acute treatment for flares, challenges or inability to work or participate in daily or family life, and anxiety and fear of disease relapse or irreversible organ damage. The input also noted the trade off of disease control versus medication side effects, some of which are particularly burdensome, especially steroid-related side effects that can be difficult to tolerate and elevate other health risks, such as worsening diabetes control. Moreover, patients who live far from specialized centres face substantial travel and time burdens, and may not consistently have the opportunity to access adequate health care, such as visiting a specialist and receiving treatments for IgG4-RD.
Equity considerations and ethical implications: The most important equity considerations and ethical implications stem from the rarity of IgG4-RD. CDEC noted several unmet nonclinical needs, including limited access to specialized care for people in rural and remote regions, which may delay diagnosis for some patients. CDEC also discussed that the IV administration of inebilizumab would necessitate travelling to a hospital or infusion centre. Overall, there is a need for more accessible treatment options and supportive services that help maintain continuity of care particularly for patients in remote areas. CDEC also noted that inequitable access to rituximab contributes to variation in care across jurisdictions.
Economic Considerations
Health impacts of inebilizumab versus relevant comparators: Compared to best supportive care (BSC), inebilizumab may be associated with a gain of 0.47 to 0.56 life-years and 0.49 to 0.71 quality-adjusted life-years (QALYs) among patients with IgG4-RD.
Cost of inebilizumab versus relevant comparators: Inebilizumab is predicted to be associated with higher costs to health care systems than BSC over a lifetime horizon (incremental costs ranged from $1,147,434 to $1,259,521), primarily driven by drug acquisition costs associated with inebilizumab.
Key findings of the economic evaluation: Based on the submitted evidence using the sponsor’s cost-utility analysis, the submitted base-case analysis estimated that the incremental cost-effectiveness ratio (ICER) for inebilizumab compared to BSC was $1,775,633 per QALY gained. Due to limitations with the structure of the sponsor’s pharmacoeconomic model, its representation of current clinical practice in Canada, and the availability of long-term evidence, CDA-AMC did not present a base case but undertook scenario analyses to highlight the impact of some limitations with the sponsor’s model. CDA-AMC estimated that the ICER for inebilizumab plus BSC compared to BSC alone falls between $1,938,171 to $2,585,721 per QALY depending on whether there are differences between modelled treatment arms in use of off-label therapies, glucocorticoid-related events, and mortality. CDEC considered all scenarios were reasonable, thus, to inform the price condition, CDEC used the scenario removing the risk of glucocorticoid-related events (Figure 1). CDEC noted that, as all scenarios were reasonable, the ICER may be higher than what was reported by CDA-AMC. CDEC considered that rituximab was a key comparator for inebilizumab as both of these treatments are B-cell depleting therapies. To ensure cost-effectiveness, CDEC discussed that inebilizumab should be negotiated so that the drug price does not exceed the least costly B-cell depleting treatment used by the population indicated for treatment with inebilizumab.
Figure 1: Estimate of the ICER Used by CDEC to Inform the Price Condition
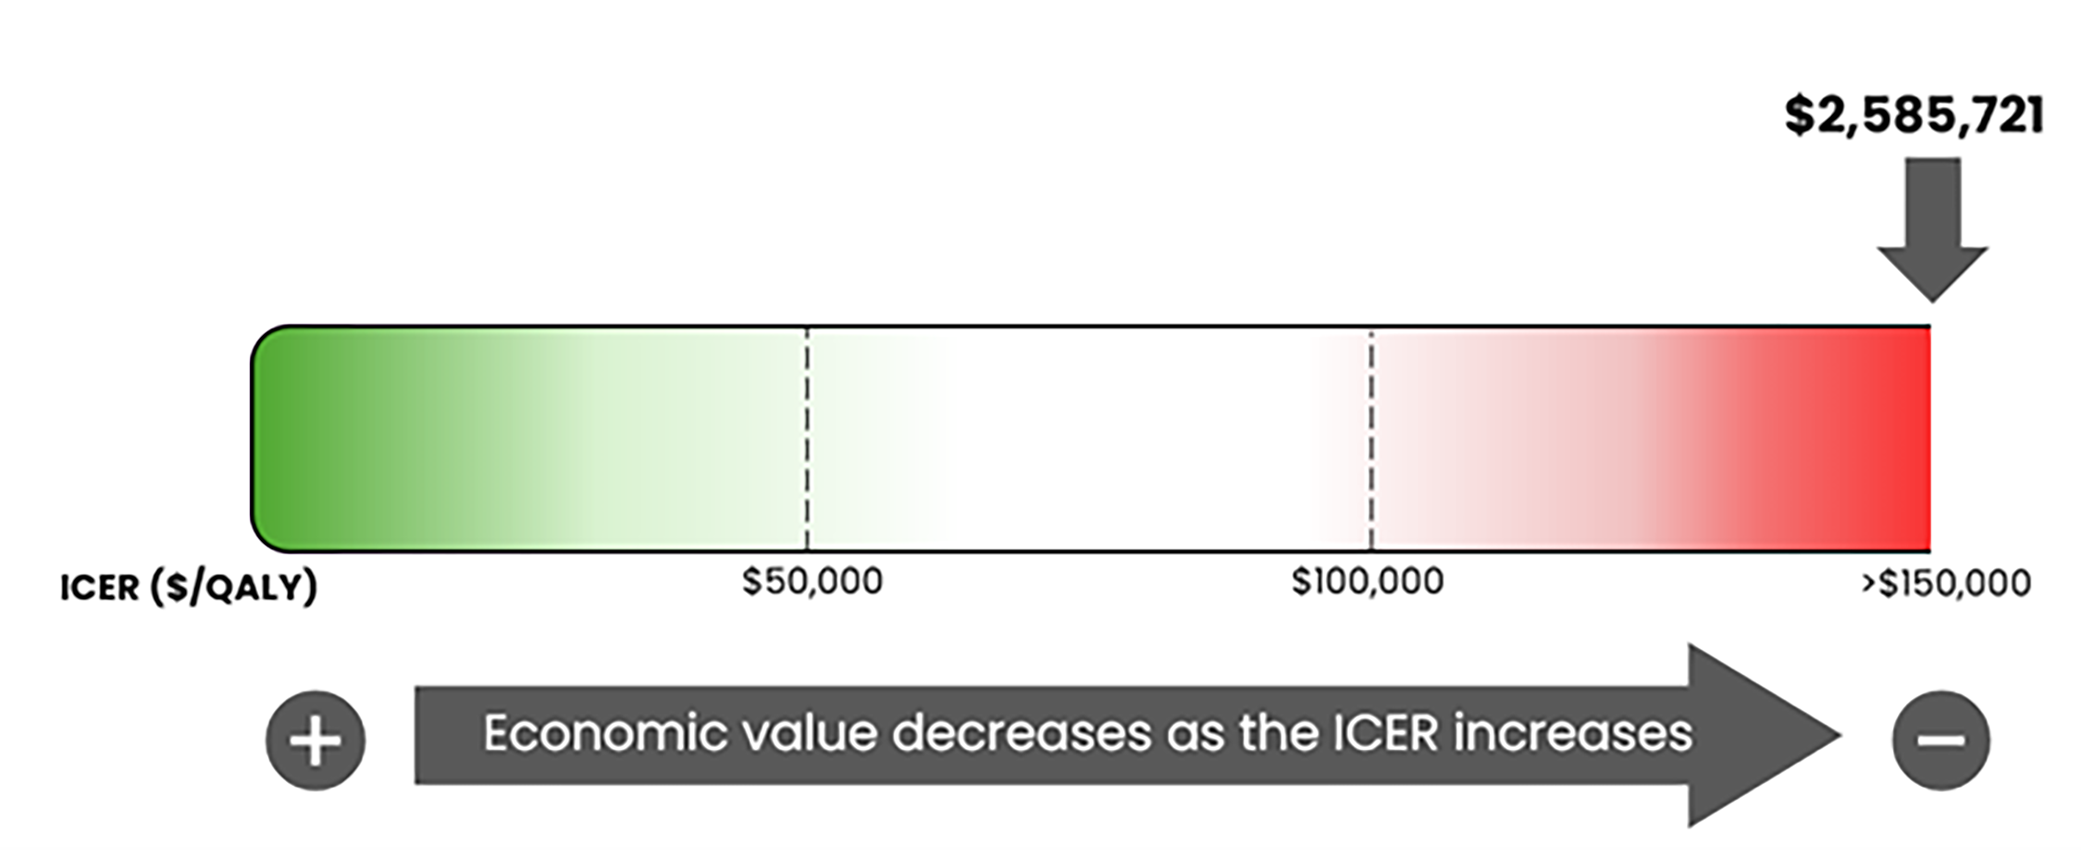
CDEC = Canadian Drug Expert Committee; ICER = incremental cost-effectiveness ratio; QALY = quality-adjusted life-year.
Certainty of the evidence: CDEC discussed that the estimated ICERs for inebilizumab are highly uncertain due to limitations in the underlying clinical evidence, model structure and assumptions, and unresolved uncertainty regarding treatment pathways in clinical practice. Given the identified limitations with the submitted model structure and uncertainty in the long-term efficacy data, the economic analysis may not accurately assess the impact of inebilizumab on patient health and health care resources. Further, the economic evaluation did not consider a stopping rule or other discontinuation criteria that aligned with the recommendation. As a result, the cost-effectiveness estimates are highly uncertain and higher price reductions may be required to achieve a given willingness-to-pay threshold.
Other considerations: CDEC noted that the cost-effectiveness of inebilizumab plus BSC versus current therapies used off label in Canada for the treatment of IgG4-RD including rituximab, immunosuppressant therapies, and low-dose prednisone is unknown given the lack of comparative efficacy data. The sponsor submitted an additional cost-effectiveness analysis adopting a societal perspective. In this analysis, the sponsor’s approach to estimating patient and caregiver productivity loss and transportation costs were uncertain due to a lack of empirical evidence and limitations in the sponsor’s estimation of indirect costs. As a result of the lack of evidence and uncertainty in the sponsor’s approach, CDA-AMC was unable to present an analysis from the societal perspective.
Impacts on Health Systems
Anticipated budget impact: CDA-AMC estimated that by year 3 of reimbursement, 479 patients would be eligible for treatment with inebilizumab of whom 321 are expected to receive inebilizumab. It is estimated that the budget impact of reimbursing inebilizumab for the treatment of IgG4-RD in adult patients will be approximately $128 million over the first 3 years of reimbursement compared to the amount currently spent on comparators, with an estimated expenditure of $129 million on inebilizumab over this period. The actual budget impact of reimbursing inebilizumab in this patient group is uncertain and will depend on the prevalence of IgG4-RD and the market uptake of inebilizumab. CDEC noted that the economic feasibility of adoption must be addressed.
Sources of Information Used by the Committee
To make its recommendation, the committee-subcommittee considered the following information (links to the full documents for the review can be found on the project webpage):
the CDA-AMC review of the clinical and pharmacoeconomic evidence submitted by the sponsor, as well as relevant ethical issues related to inebilizumab (refer to the Main Report and Supplemental Material document)
the sponsor’s comments on the draft report and the CDA-AMC responses
patients' perspectives gathered by 4 patient groups: Vasculitis Foundation Canada and the Colorectal Cancer Resource & Action Network; Arthritis Consumer Experts; The Sumaira Foundation; and the Canadian Organization for Rare Disorders (refer to the Patient and Clinician Group Input document)
input from a person with lived experience who delivered a brief presentation and answered questions from the committee (refer to the Person With Lived Experience section in this document)
input from 3 clinician groups: the Canadian Rheumatology Association; the Autoimmune and Rare Liver Disease Programme, Toronto General Hospital; and CanVasc and Canadian MD colleagues with interest in IgG4-RD (refer to the Patient and Clinician Group Input document)
input from public drug programs that participate in the reimbursement review process (refer to the Supplemental Material document)
input from 3 clinical experts with expertise in the management of IgG4-RD consulted by CDA-AMC.
Special thanks: CDA-AMC extends our special thanks to the individual who presented directly to CDEC, those living with IgG4-RD.
General note: CDA-AMC makes every attempt to engage with people with lived experience as closely to the indication under review as possible; however, at times, CDA-AMC is unable to do so and instead engages with individuals with similar treatment journeys to ensure lived experience perspectives are included and considered in Reimbursement Reviews. CDA-AMC is fortunate to be able to engage with individuals who are willing to share their treatment journeys with CDEC-pERC.
CDEC Information
Members of the Committee
Dr. Peter Jamieson (Chair), Dr. Kerry Mansell (Vice-Chair), Sally Bean, Daryl Bell, Dan Dunsky, Dr. Ran Goldman, Dr. Trudy Huyghebaert, Dr. Dennis Ko, Dr. Christine Leong, Alicia McCallum, Dr. Srinivas Murthy, Dr. Nicholas Myers, Dr. Krishnan Ramanathan, Dr. Marco Solmi, Carla Velastegui, Dr. Edward Xie, and Dr. Peter Zed.
Meeting date: July 23, 2026
Regrets: None
Conflicts of interest: None
ISSN: 2563-6596
Canada’s Drug Agency (CDA-AMC) is a pan-Canadian health organization. Created and funded by Canada’s federal, provincial, and territorial governments, we’re responsible for driving better coordination, alignment, and public value within Canada’s drug and health technology landscape. We provide Canada’s health system leaders with independent evidence and advice so they can make informed drug, health technology, and health system decisions, and we collaborate with national and international partners to enhance our collective impact.
Disclaimer: CDA-AMC has taken care to ensure that the information in this document was accurate, complete, and up to date when it was published, but does not make any guarantee to that effect. Your use of this information is subject to this disclaimer and the Terms of Use at cda-amc.ca.
The information in this document is made available for informational and educational purposes only and should not be used as a substitute for professional medical advice, the application of clinical judgment in respect of the care of a particular patient, or other professional judgments in any decision-making process. You assume full responsibility for the use of the information and rely on it at your own risk.
CDA-AMC does not endorse any information, drugs, therapies, treatments, products, processes, or services. The views and opinions of third parties published in this document do not necessarily reflect those of CDA-AMC. The copyright and other intellectual property rights in this document are owned by the Canadian Agency for Drugs and Technologies in Health (operating as CDA-AMC) and its licensors.
Questions or requests for information about this report can be directed to Requests@CDA-AMC.ca