Drugs, Health Technologies, Health Systems
Reimbursement Recommendation
Pembrolizumab (Keytruda)
Indication: Pembrolizumab, in combination with enfortumab vedotin, as neoadjuvant treatment and then continued after radical cystectomy as adjuvant treatment, is indicated for the treatment of adult patients with MIBC who are ineligible for cisplatin-containing chemotherapy.
Sponsor: Merck Canada Inc.
Final recommendation: Reimburse with conditions
Summary
What Is the Reimbursement Recommendation for Keytruda?
Canada’s Drug Agency (CDA-AMC) recommends that Keytruda, in combination with enfortumab vedotin, be reimbursed by public drug plans for the treatment of muscle invasive bladder cancer (MIBC) as neoadjuvant treatment and then continued after radical cystectomy as adjuvant treatment, if certain conditions are met.
Why Did CDA-AMC Recommend Reimbursement?
The pan-Canadian Oncology Drug Review Expert Review Committee (pERC) determined that perioperative enfortumab vedotin plus Keytruda demonstrates acceptable clinical value versus surgery alone in patients with MIBC who are ineligible for cisplatin-containing chemotherapy. This determination was enough for pERC to recommend that Keytruda, in combination with enfortumab vedotin, be reimbursed. Given that enfortumab vedotin plus Keytruda is expected to be an additive treatment to surgery, acceptable clinical value refers to added value versus surgery alone.
Evidence from 1 clinical trial (KEYNOTE-905) showed that perioperative enfortumab vedotin plus Keytruda and surgery improved overall survival (OS) and event-free survival (EFS) at 24 months, as well as a likely improvement in the pathological complete response rate versus radical cystectomy plus pelvic lymph node dissection (surgery alone) in patients with MIBC who are ineligible for cisplatin-containing chemotherapy.
Which Patients Are Eligible for Coverage?
Keytruda, in combination with enfortumab vedotin, should only be covered when used as neoadjuvant treatment in adults with a confirmed diagnosis of MIBC who are eligible for surgery, ineligible for cisplatin-based chemotherapy, have not received previous treatment for MIBC, and have good performance status.
What Are the Conditions for Reimbursement?
Keytruda, in combination with enfortumab vedotin, should continue to be reimbursed only when used as adjuvant treatment after neoadjuvant treatment and bladder surgery have been completed and the total program cost of Keytruda is reduced. Adjuvant treatment should start within 6 months after surgery, and there should be no evidence of disease progression. Treatment should be stopped if there is disease progression, if adverse effects become unacceptable, or if the patient has received the maximum number of treatment cycles. Keytruda in combination with enfortumab vedotin should be prescribed by clinicians who have expertise and experience in treating bladder cancer.
Review Background
Disease background:
MIBC is a serious type of bladder cancer in which the tumour has grown into the muscle layer of the bladder. This makes it more likely to spread to other parts of the body.
In 2022, the estimated number of people living with bladder cancer in Canada within the previous 2 years was 17,595 and within the previous 5 years was 37,315.
Among patients diagnosed with bladder cancer, an estimated 25% have MIBC.
Indication and reimbursement request: Pembrolizumab (Keytruda), in combination with enfortumab vedotin, has been approved by Health Canada as neoadjuvant treatment and then continued after radical cystectomy as adjuvant treatment for the treatment of adult patients with MIBC who are ineligible for cisplatin-containing chemotherapy. The sponsor is seeking reimbursement for this patient population.
Drug under review: Pembrolizumab is a monoclonal antibody and is administered by IV infusion.
In the neoadjuvant setting, the dosage recommended in the product monograph is pembrolizumab 200 mg every 3 weeks for 3 doses in combination with enfortumab vedotin 1.25 mg/kg on days 1 and 8 of each 21-day cycle for 3 cycles or until disease progression that precludes radical cystectomy or unacceptable toxicity.
In the adjuvant setting, the dosage recommended in the product monograph is pembrolizumab 200 mg every 3 weeks for 14 doses or 400 mg every 6 weeks for 7 doses in combination with enfortumab vedotin 1.25 mg/kg on days 1 and 8 of each 21-day cycle for 6 cycles or until disease recurrence or unacceptable toxicity.
Treatment costs: At the submitted price of $4,400.00 per 100 mg/4 mL vial, the cost of pembrolizumab per 28-days is expected to be $11,733 per patient using a fixed dosage (200 mg once every 3 weeks) and $8,917 using a weight-based dosage (2 mg/kg [up to 200 mg] once every 3 weeks per patient), based on the Health Canada–recommended dosage. When pembrolizumab is used in combination with enfortumab vedotin, the expected 28-day cost is $25,097 per patient using fixed dosage and $22,281 per patient using weight-based dosage.
Highlights of Input From Interested Parties
The patient group (Bladder Cancer Canada) noted the following regarding impacts of the disease, unmet needs, and important outcomes:
The most common symptoms of MIBC include hematuria, urinary frequency, and urinary urgency. Additional symptoms include fatigue, dysuria, and back pain.
There is an unmet clinical need for effective neoadjuvant and adjuvant therapies to improve survival while maintaining a manageable safety profile and health-related quality of life (HRQoL), and that can be administered to patients who are unable to receive cisplatin-based chemotherapy due to impaired renal function or other comorbidities.
The most important treatment goals are to control disease progression and prevent recurrence. Additional important outcomes include maintaining HRQoL, managing adverse effects, and alleviating symptoms of the disease.
The clinician groups (British Columbia Genitourinary Tumour Group and Ontario Health [Cancer Care Ontario] Genitourinary Cancer Drug Advisory Committee) and the clinical experts consulted by CDA-AMC noted the following regarding unmet needs arising from the disease, important outcomes, and place in therapy for the drug under review:
The unmet clinical need identified by the clinician groups and the clinical experts consulted align with those identified by the patient group.
The most important treatment goal is to improve survival outcomes in patients who are not eligible to receive cisplatin, but also for all patients with MIBC. Additional important goals include providing a disease-modifying neoadjuvant treatment option, reducing micrometastatic disease burden before surgery, increasing pathological complete response (pCR) rates, improving EFS, reducing the risk of distant metastatic recurrence, and improving tolerability in an older, comorbid patient population.
The anticipated place in therapy of enfortumab vedotin plus pembrolizumab will be the new standard of care for patients with MIBC who have contraindications to cisplatin-based combination therapy and undergo upfront surgical management without receiving systemic therapy in the preoperative setting.
The participating public drug programs raised potential implementation issues related to considerations for initiation, discontinuation, and prescribing of therapy; generalizability of trial populations to broader populations; system and economic issues; and potential need for a provisional funding algorithm.
Recommendation
With a vote of 15 to 0, pERC recommends that pembrolizumab be reimbursed for the treatment of adult patients with MIBC who are ineligible for cisplatin-containing chemotherapy, in combination with enfortumab vedotin, as neoadjuvant treatment and then continued after radical cystectomy as adjuvant treatment, only if the conditions listed in Table 1 are met.
Table 1: Reimbursement Conditions and Reasons
Reimbursement condition | Reason | Implementation guidance |
|---|---|---|
Initiation | ||
1. Treatment with pembrolizumab in combination with enfortumab vedotin as neoadjuvant treatment should be initiated in adult patients who are eligible for surgery, who meet all of the following criteria: 1.1. have histologically confirmed urothelial-MIBC (clinical stage T2-T4aN0M0 or T1-T4aN1M0) 1.2. have not received prior systemic chemotherapy or immunotherapy for treatment of MIBC 1.3. ineligible for cisplatin-based chemotherapy. | Evidence from the KEYNOTE-905 trial demonstrated that treatment with enfortumab vedotin plus pembrolizumab and surgery resulted in a clinical benefit compared with surgery alone in patients with these characteristics. | In the KEYNOTE-905 trial, patients were considered ineligible for cisplatin-based chemotherapy if they met 1 of the following:
pERC agreed with the experts that patients who do not meet the listed criteria for impaired renal function may still be considered eligible for treatment with enfortumab vedotin plus pembrolizumab at the clinician’s discretion and/or based on specialist evaluation. |
2. Patients should have an ECOG PS score of 0 to 2. | Patients with an ECOG PS score of 0 to 2 were included in the KEYNOTE-905 trial. | — |
Renewal (continuation with adjuvant therapy) | ||
3. Continued reimbursement of adjuvant treatment with pembrolizumab in combination with enfortumab vedotin should be based on meeting all of the following criteria: 3.1. completion of neoadjuvant pembrolizumab in combination with enfortumab vedotin 3.2. completion of a surgical procedure for the bladder 3.3. initiation of adjuvant therapy no more than 6 months after surgery with no evidence of disease progression. | In the KEYNOTE-905 trial, patients were required to undergo a radical cystectomy to continue with adjuvant enfortumab vedotin plus pembrolizumab. In the KEYNOTE-905 trial, patients received postoperative enfortumab vedotin plus pembrolizumab at 8 weeks (56 days ± 14 days) after radical cystectomy plus pelvic lymph node dissection per protocol. However, starting treatment no more than 6 months after surgery is considered appropriate based on expert opinion. | pERC noted that adjuvant enfortumab vedotin plus pembrolizumab therapy is not recommended for patients who have completed surgery without receiving neoadjuvant enfortumab vedotin plus pembrolizumab due to a lack of supporting data. pERC agreed with the clinical experts that a bladder-sparing alternative to radical cystectomy, such as trimodal therapy, should not limit eligibility for adjuvant treatment with enfortumab vedotin plus pembrolizumab. pERC agreed with the clinical experts, who indicated that immunotherapy-based re-treatment for relapsed or metastatic disease (including enfortumab vedotin plus pembrolizumab) may be appropriate for patients with a disease-free interval of at least 6 months after completing adjuvant enfortumab vedotin plus pembrolizumab. |
Discontinuation | ||
4. Neoadjuvant treatment with pembrolizumab in combination with enfortumab vedotin, followed by adjuvant pembrolizumab in combination with enfortumab vedotin, should be discontinued upon the occurrence of any of the following: 4.1. disease progression 4.2. unacceptable toxicity 4.3. maximum number of 9 cycles of enfortumab vedotin (3 as neoadjuvant and 6 as adjuvant) and 17 cycles of pembrolizumab (3 as neoadjuvant and 14 as adjuvant). | In the KEYNOTE-905 trial, treatment was discontinued upon disease progression or unacceptable toxicity, which is consistent with clinical practice. Patients in the KEYNOTE-905 trial received pembrolizumab in combination with enfortumab vedotin for a maximum of 17 cycles:
| pERC agreed with the clinical experts, who indicated that it would be appropriate to continue pembrolizumab or enfortumab vedotin if 1 of the treatments had to be discontinued. At least 1 cycle of enfortumab vedotin should be administered with pembrolizumab in the neoadjuvant setting to be eligible for continued pembrolizumab monotherapy. |
Prescribing | ||
5. Neoadjuvant treatment with pembrolizumab in combination with enfortumab vedotin, followed by adjuvant pembrolizumab in combination with enfortumab vedotin, should be prescribed by clinicians with expertise and experience in treating bladder cancer. | This is meant to ensure that pembrolizumab is prescribed for the appropriate patients and that adverse effects are managed in an optimized and timely manner. | pERC noted that jurisdictions may consider implementing weight-based dosing up to a cap for pembrolizumab (e.g., 2 mg/kg up to 200 mg [every 3 weeks]). |
Pricing | ||
6. A reduction in price. | Using the CDA-AMC base-case analysis, the ICER for enfortumab vedotin plus pembrolizumab and surgery was $3,247 per QALY gained when compared with surgery with or without adjuvant nivolumab in the indicated population. No price reduction would be required to achieve cost-effectiveness at a $50,000 or $100,000 per QALY threshold. Exact price reductions at any given willingness-to-pay threshold can be found in the CDA-AMC Main Report and Supplemental Material document. | The CDA-AMC analysis is based on public list prices for all treatments. Further price reductions may be required if there are price arrangements (discounts) currently in place for any treatment included in the economic analysis. |
CDA-AMC = Canada’s Drug Agency; ECOG PS = European Cooperative Oncology Group Performance Status; ICER = incremental cost-effectiveness ratio; MIBC = muscle invasive bladder cancer; NYHA = New York Heart Association; pERC = pan-Canadian Oncology Drug Review Expert Review Committee; QALY = quality-adjusted life-year.
Rationale for the Recommendation
Clinical Value
Based on the totality of the clinical evidence, pERC concluded that perioperative enfortumab vedotin plus pembrolizumab demonstrates acceptable clinical value compared with surgery alone in patients with MIBC who are ineligible for cisplatin-containing chemotherapy. Given that enfortumab vedotin plus pembrolizumab is expected to be an additive treatment to surgery, acceptable clinical value refers to added value versus surgery alone.
Evidence from 1 randomized controlled trial (KEYNOTE-905; N = 344) demonstrated that treatment with perioperative enfortumab vedotin plus pembrolizumab and surgery results in added clinical benefit for patients with MIBC who are ineligible for cisplatin-containing chemotherapy compared with radical cystectomy plus pelvic lymph node dissection (surgery alone) in EFS and OS at 24 months. Enfortumab vedotin plus pembrolizumab and surgery was favoured over surgery alone based on EFS (hazard ratio [HR] = 0.40; 95% confidence interval [CI], 0.28 to 0.57; P < 0.0001). Enfortumab vedotin plus pembrolizumab and surgery was favoured over surgery alone based on OS (HR = 0.50; 95% CI, 0.33 to 0.74; P = 0.0002). Enfortumab vedotin plus pembrolizumab and surgery likely results in an increase in the pCR rate when compared with surgery alone. The pCR rate was 57.1% (95% CI, 49.3% to 64.6%) in the enfortumab vedotin plus pembrolizumab and surgery group and 8.6% (95% CI, 4.9% to 13.8%) in the surgery alone group.
In the KEYNOTE-905 study, treatment with enfortumab vedotin plus pembrolizumab and surgery was associated with a greater number of adverse events compared with surgery alone; however, no new safety signals were identified, and the committee considered the harms reported significant but manageable through standard clinical practices and established guidelines.
Patients and clinicians identified the need for effective treatment options that improve survival while maintaining a manageable safety profile and HRQoL. pERC concluded that, compared to surgery alone, treatment with perioperative enfortumab vedotin plus pembrolizumab and surgery addresses some of the identified unmet needs by improving OS and demonstrating a manageable safety profile. The impact of perioperative enfortumab vedotin plus pembrolizumab and surgery on HRQoL compared to surgery alone was not valid to draw a conclusion due to multiple sources of bias.
Further information on the committee’s discussion around clinical value is provided in the Summary of Deliberation section.
Developing the Recommendation
The determination of acceptable clinical value was sufficient for pERC to recommend reimbursement of enfortumab vedotin plus pembrolizumab. As part of the deliberation on whether to recommend reimbursement, the committee also considered unmet clinical need, unmet nonclinical need, and health inequity. Information on this discussion is provided in the Unmet Clinical Need and Distinct Social and Ethical Considerations domains in the Summary of Deliberation section.
Because pERC recommended that enfortumab vedotin plus pembrolizumab be reimbursed, the committee also deliberated on whether reimbursement conditions should be added to address important economic considerations, health system impacts, or social and ethical considerations, or to ensure clinical value is realized. The resulting reimbursement conditions, with accompanying reasons and implementation guidance, are stated in Table 1.
Summary of Deliberation
pERC considered all domains of value of the deliberative framework before developing its recommendation: clinical value, unmet clinical need, distinct social and ethical considerations, economic considerations, and impacts on health systems. For further information on the domains of value, refer to Expert Committee Deliberation at Canada’s Drug Agency.
The committee considered the following key discussion points, organized by the 5 domains of value.
Clinical Value
Appropriate comparators: The committee considered radical cystectomy plus pelvic lymph node dissection with or without adjuvant nivolumab to be appropriate comparators for perioperative pembrolizumab, in combination with enfortumab vedotin, in patients with MIBC who are not eligible to receive cisplatin-containing chemotherapy.
Efficacy versus radical cystectomy plus pelvic lymph node dissection with or without adjuvant nivolumab: One ongoing phase III, multicentre, parallel-group, open-label, randomized controlled trial (KEYNOTE-905; N = 344) provided evidence for the efficacy and safety of perioperative enfortumab vedotin plus pembrolizumab plus radical cystectomy plus pelvic lymph node dissection (“enfortumab vedotin plus pembrolizumab and surgery”) versus radical cystectomy plus pelvic lymph node dissection (“surgery alone”) in patients with clinical stage T2-T4aN0M0 or T1-T4aN1M0 MIBC who are not eligible to receive or decline cisplatin-based chemotherapy. The trial demonstrated that treatment with enfortumab vedotin plus pembrolizumab and surgery resulted in a clinically important increase in the probability of EFS (based on blinded independent central review assessment) and OS at 24 months compared with surgery alone. The EFS rate at 24 months in the enfortumab vedotin plus pembrolizumab and surgery group was 74.7% (95% CI, 66.9% to 80.8%) and in the surgery alone group was 39.4% (95% CI, 31.0% to 47.8%). The OS rate at 24 months in the enfortumab vedotin plus pembrolizumab and surgery group was 79.7% (95% CI, 72.5% to 85.3%) and in the surgery alone group was 63.1% (95% CI, 54.7% to 70.4%). The KEYNOTE-905 trial also demonstrated that treatment with enfortumab vedotin plus pembrolizumab and surgery resulted in a likely clinically important increase in pCR rate (based on the blinded independent central review assessment) compared with surgery alone. Patients who were not eligible to receive cisplatin comprised approximately 80% of the study population and the study population was representative of patients with MIBC in clinical practice. Prespecified subgroup analyses by cisplatin eligibility for EFS, OS, and pCR rate were generally consistent with the overall treatment effects observed in the main analysis. Data from the KEYNOTE-905 trial were not valid to draw conclusions about impacts on HRQoL.
Clinical importance of treatment effects: The committee acknowledged that controlling disease progression, preventing recurrence, maintaining HRQoL, managing adverse effects, and alleviating symptoms of the disease are important outcomes to patients. The committee acknowledged that closing the survival gap between patients who are eligible to receive cisplatin- and those who are not eligible to receive cisplatin is an important treatment goal, as noted by clinicians and the clinical experts consulted. The committee considered the treatment effects to be clinically important to a degree that justifies a positive recommendation despite the uncertainty in the outcome of HRQoL, noting that the OS benefit was supported by findings in the surrogate end points of EFS and pCR rate.
Certainty of the evidence: For the comparison of enfortumab vedotin plus pembrolizumab and surgery versus surgery alone, the KEYNOTE-905 trial demonstrated a clinically important increase in the probability of OS and EFS at 24 months (high certainty per Grading of Recommendations Assessment, Development and Evaluation [GRADE] assessment), and a likely clinically important increase in pCR rates (moderate certainty per GRADE assessment). The committee noted that these findings are derived from an interim analysis. The median was not reached for either of EFS and OS in the enfortumab vedotin plus pembrolizumab and surgery group. While interim analysis results remain subject to change with further follow-up, based on visual assessment, the Kaplan-Meier curves separated early in the trial and there did not appear to be a serious violation of the proportional hazards assumption, suggesting that subsequent overlap is unlikely. The committee considered the level of certainty in the clinical evidence to be at a degree that supports a positive recommendation, despite the findings being derived from an interim analysis.
Comparative harms: The KEYNOTE-905 trial showed that treatment with enfortumab vedotin plus pembrolizumab and surgery was associated with a greater number of adverse events compared with surgery alone; however, no new safety signals were identified, and the committee considered the harms to be significant but manageable through standard clinical practices and established guidelines.
Subpopulation (eligible to receive but declined cisplatin): pERC acknowledged that patients, clinicians, and the clinical experts consulted indicated that there are patients who are eligible to receive but decline cisplatin-based chemotherapy who may prefer enfortumab vedotin plus pembrolizumab and surgery as a treatment option. The committee noted that while 20% of the KEYNOTE-905 trial population were enrolled under the expanded inclusion criteria that included patients who are eligible to receive but declined cisplatin-based chemotherapy, the Health Canada–approved indication is for the treatment of adult patients with MIBC who are ineligible to receive cisplatin-containing chemotherapy. As such, this subpopulation falls outside the scope of the sponsor’s submission and the focus of the CDA-AMC review. Further, the scope of the sponsor’s submission did not include relevant comparators for patients who are eligible to receive cisplatin-based therapy at this time. pERC also acknowledged the KEYNOTE-B15 study that evaluated perioperative enfortumab vedotin plus pembrolizumab versus neoadjuvant gemcitabine and cisplatin in patients with MIBC who are eligible to receive cisplatin; however, this trial was not included in the sponsor’s systematic review and it was not aligned with the Health Canada indication informing the scope of the current submission.
Clinical value: Based on all of the preceding considerations, the committee determined there was added clinical value versus appropriate comparators (surgery alone).
Unmet Clinical Need
Input on unmet clinical need: Patients, clinicians, and the clinical experts consulted identified a need for effective neoadjuvant and adjuvant therapies to improve survival while maintaining a manageable safety profile and HRQoL, and that can be administered to patients who are unable to receive cisplatin-based chemotherapy due to impaired renal function or other comorbidities.
Severity of the disease: The committee considered MIBC to be a serious and potentially life-threatening condition, noting that the estimated 5-year mortality in 2019 was approximately 40% to 50% in Canada. The committee acknowledged the impacts of the disease from the patient perspective, noting that common symptoms of MIBC include hematuria, urinary frequency, urinary urgency, fatigue, dysuria, and back pain.
Availability of treatment options: Patients with MIBC who have contraindications to cisplatin-based chemotherapy proceed directly to radical local therapy. According to the patient group, clinician groups, and the clinical experts consulted, these patients do not receive disease-modifying systemic therapy in the preoperative setting because there is currently no approved neoadjuvant systemic treatment option in Canada for this population. Clinicians and the clinical experts consulted noted that while surgery can remove localized tumour burden, it does not eradicate occult metastatic disease or reduce the risk of distant recurrence before dissemination. Clinicians and the clinical experts consulted further noted that adjuvant nivolumab is limited to patients at high risk of recurrence. Clinicians and the clinical experts consulted emphasized that these patients remain at high risk of recurrence and micrometastatic disease and experience poor survival outcomes following cystectomy alone.
Distinct Social and Ethical Considerations
Input on unmet nonclinical need: The committee acknowledged input from the clinical experts consulted, who noted that perioperative enfortumab vedotin plus pembrolizumab may be less commonly considered in rural settings, as many centres are not equipped to manage its associated toxicities. The committee further acknowledged input from the clinician groups, who noted that given the known complications associated with enfortumab vedotin plus pembrolizumab, initial treatment should be administered in centres where there is experience with managing the risk of extravasation.
Ethical implications: Although there is no evidence beyond expert opinion to inform radical cystectomy versus bladder-sparing approaches as a condition for reimbursement, the committee acknowledged the clinical importance of increasing the opportunity for bladder-sparing approaches to patients. The committee further acknowledged the impacts of radical cystectomy, which is associated with high morbidity and can cause permanent changes to urinary function, including the need to live with a urostomy, as well as changes in body image, self-esteem, and sexual function. The committee deferred to the input from the clinical experts consulted who noted that patients should be offered a choice between radical cystectomy and bladder-sparing approaches, such as trimodal therapy, without having to forgo potential survival benefits from adjuvant treatment if bladder preservation is preferred. The clinical experts further noted that if pCR is achieved following neoadjuvant therapy, with no evidence of disease in the bladder, removal of the bladder should not be mandated as a condition for reimbursement of the remainder of the treatment regimen.
Economic Considerations
Health impacts of enfortumab vedotin plus pembrolizumab and surgery versus relevant comparators: Enfortumab vedotin plus pembrolizumab and surgery is predicted to be associated with a gain of 3.19 life-years and may result in a gain of 2.69 quality-adjusted life-years (QALYs) compared to surgery with or without adjuvant nivolumab over lifetime (28 year) horizon.
Cost of enfortumab vedotin plus pembrolizumab and surgery versus relevant comparators: Enfortumab vedotin plus pembrolizumab and surgery is predicted to be associated with higher costs to health care systems than surgery with or without adjuvant nivolumab (incremental costs = $8,750) over lifetime (28 year) horizon. The increased health care costs are primarily associated with initial treatment drug acquisition costs (incremental initial drug costs = $91,360), which are offset by decreased drug costs of subsequent therapies ($71,520 in cost offsets) due to avoided disease progression for patients treated with enfortumab vedotin plus pembrolizumab and surgery.
Key findings of the economic evaluation: Based on the submitted evidence using the sponsor’s cost-utility analysis, the CDA-AMC base-case analysis estimated that the incremental cost-effectiveness ratio for enfortumab vedotin plus pembrolizumab and surgery in adult patients with MIBC who are ineligible for cisplatin-containing chemotherapy was $3,247 per QALY gained when compared with surgery with or without adjuvant nivolumab (Figure 1).
Figure 1: Estimate of the ICER Used by pERC to Inform the Price Condition
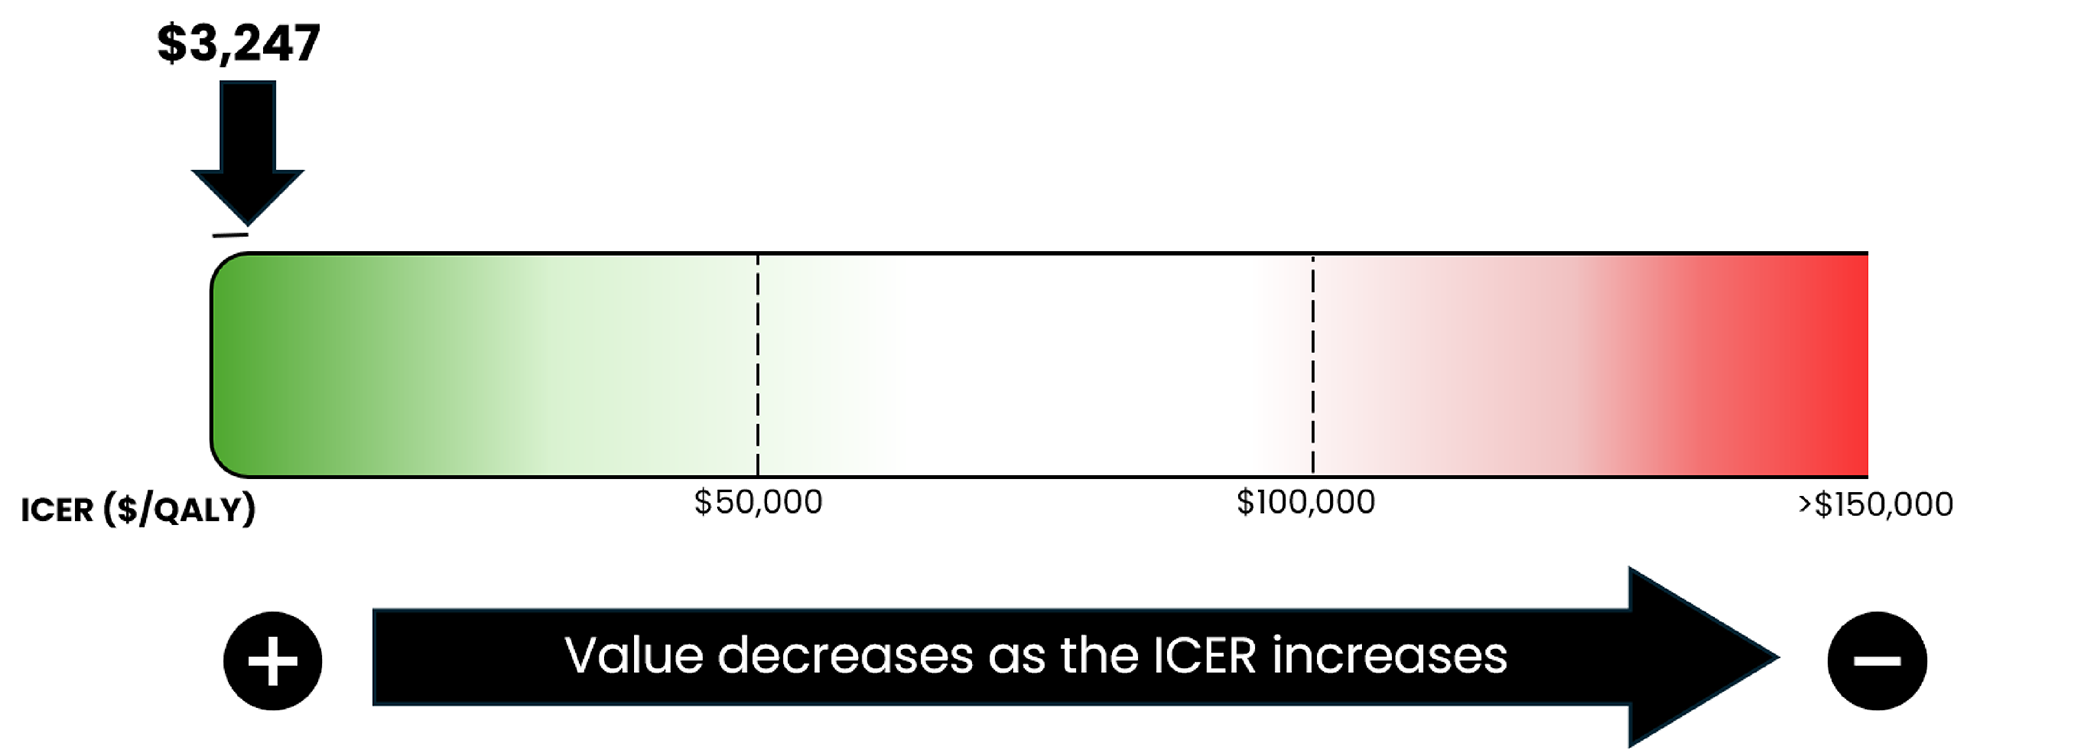
ICER = incremental cost-effectiveness ratio; QALY = quality-adjusted life-year.
Certainty of the evidence: The long-term efficacy of enfortumab vedotin plus pembrolizumab remains uncertain due to lack of long-term data. Approximately 85% of the incremental QALYs were estimated based on extrapolations beyond the trial period. pERC discussed additional uncertainty with the costs of subsequent treatments due to uncertainty in the long-term progression events predicted by the cost-utility analysis.
Other considerations: The KEYNOTE-905 trial population included patients with MIBC who are eligible for but decline cisplatin-containing chemotherapy, whereas the Health Canada indication is limited to patients who were not eligible to receive cisplatin. The cost-effectiveness versus enfortumab vedotin plus pembrolizumab was not evaluated in patients who are eligible for cisplatin-based regimens but decline it as it is out of the scope of this review. The cost-effectiveness of enfortumab vedotin plus pembrolizumab in patients who are eligible but decline it is unknown. The committee discussed there is uncertainty in the effectiveness and costs about enfortumab vedotin plus pembrolizumab use in patients who forgo surgery or patients that receive bladder-sparing surgery which were not assessed in the economic analysis due to lack of submitted evidence in this population. The cost-effectiveness of enfortumab vedotin plus pembrolizumab in patients that receive bladder-sparing surgery is unknown.
Impacts on Health Systems
Anticipated budget impact: CDA-AMC estimates that the budget impact of reimbursing enfortumab vedotin plus pembrolizumab for the indicated population will be approximately $49 million over the first 3 years of reimbursement compared to the amount currently spent on comparators. The expenditure on pembrolizumab in neoadjuvant and adjuvant setting is predicted to be $43.6 million (enfortumab vedotin plus pembrolizumab = $88.8 million) over this period. The actual budget impact of reimbursing pembrolizumab will depend on the proportion of the patients who undergo surgery in practice, and the market share of enfortumab vedotin plus pembrolizumab and surgery. The committee discussed there is uncertainty in the number of patients eligible to receive enfortumab vedotin plus pembrolizumab and surgery, which could impact the estimated budget impact.
Sources of Information Used by the Committee
To make its recommendation, the committee considered the following information (links to the full documents for the review can be found on the project webpage on the CDA-AMC website):
the CDA-AMC review of the clinical and pharmacoeconomic evidence submitted by the sponsor, as well as relevant ethical issues related to pembrolizumab (refer to the Main Report and Supplemental Material document)
the sponsor’s comments on the draft report and the CDA-AMC responses
patients' perspectives gathered by 1 patient group, Bladder Cancer Canada (refer to the Patient and Clinician Group Input document)
input from 2 clinician groups, British Columbia Genitourinary Tumour Group and Ontario Health (Cancer Care Ontario) Genitourinary Cancer Drug Advisory Committee (refer to the Patient and Clinician Group Input document)
input from the public drug programs that participate in the reimbursement review process (refer to the Supplemental Material document)
input from 2 clinical experts with expertise in the management of MIBC consulted by CDA-AMC.
pERC Information
Members of the Committee
Dr. Catherine Moltzan (Chair), Dr. Kelvin Chan (Vice-Chair), Paul Agbulu, Dr. Phillip Blanchette, Dr. Matthew Cheung, Annette Cyr, Dr. Jennifer Fishman, Dr. Prafull Ghatage, Dr. Jason Hart, Terry Hawrysh, Dr. Yoo-Joung Ko, Dr. Aly-Khan Lalani, Amy Peasgood, Dr. Anca Prica, Dr. Michael Raphael, Dr. Adam Raymakers, Dr. Patricia Tang, Dr. Pierre Villeneuve, and Danica Wasney.
Meeting date: July 9, 2026
Regrets: Two expert committee members did not attend.
Conflicts of interest: One expert committee member did not participate due to considerations of conflict of interest.
ISSN: 2563-6596
Canada’s Drug Agency (CDA-AMC) is a pan-Canadian health organization. Created and funded by Canada’s federal, provincial, and territorial governments, we’re responsible for driving better coordination, alignment, and public value within Canada’s drug and health technology landscape. We provide Canada’s health system leaders with independent evidence and advice so they can make informed drug, health technology, and health system decisions, and we collaborate with national and international partners to enhance our collective impact.
Disclaimer: CDA-AMC has taken care to ensure that the information in this document was accurate, complete, and up to date when it was published, but does not make any guarantee to that effect. Your use of this information is subject to this disclaimer and the Terms of Use at cda-amc.ca.
The information in this document is made available for informational and educational purposes only and should not be used as a substitute for professional medical advice, the application of clinical judgment in respect of the care of a particular patient, or other professional judgments in any decision-making process. You assume full responsibility for the use of the information and rely on it at your own risk.
CDA-AMC does not endorse any information, drugs, therapies, treatments, products, processes, or services. The views and opinions of third parties published in this document do not necessarily reflect those of CDA-AMC. The copyright and other intellectual property rights in this document are owned by the Canadian Agency for Drugs and Technologies in Health (operating as CDA-AMC) and its licensors.
Questions or requests for information about this report can be directed to Requests@CDA-AMC.ca