Drugs, Health Technologies, Health Systems
Reimbursement Recommendation
Cemiplimab (Libtayo)
Indication: The adjuvant treatment of patients with cutaneous squamous cell carcinoma (CSCC) at high risk of recurrence after surgery and radiation
Sponsor: Regeneron Canada Company
Final recommendation: Reimburse with conditions
Summary
What Is the Reimbursement Recommendation for Libtayo?
Canada’s Drug Agency (CDA-AMC) recommends that Libtayo (cemiplimab) be reimbursed by public drug plans as adjuvant therapy for adults with cutaneous squamous cell carcinoma (CSCC) at high risk of recurrence after surgery and radiation, and if certain conditions are met.
Why Did CDA-AMC Recommend Reimbursement?
The pan-Canadian Oncology Drug Review Expert Review Committee (pERC) determined that Libtayo demonstrates acceptable clinical value versus active surveillance as adjuvant treatment in patients with CSCC at high risk of recurrence after surgery and radiation. This determination was enough for pERC to recommend that Libtayo be reimbursed. Given that Libtayo is expected to be an additive treatment to active surveillance, acceptable clinical value refers to added value versus active surveillance.
Evidence from a clinical trial (C-POST; N = 415) showed that treatment with Libtayo over 48 weeks improved disease-free survival (DFS) versus placebo (active surveillance) in patients with CSCC at high risk for disease recurrence who have had prior surgery and radiation therapy. However, the committee was unable to conclude that Libtayo extends patients’ lives.
Libtayo meets some of the needs identified by patients, providing an additional treatment option that reduces the risk of disease recurrence and has manageable side effects. However, pERC could not conclude that Libtayo results in improved quality of life (QoL).
Which Patients Are Eligible for Coverage?
Libtayo should only be covered for adult patients with CSCC who have completed surgery and radiation and are at high risk for their disease returning, in line with the Health Canada indication. Patients should also have good performance status and must not have received prior solid-organ transplant, stem cell transplant, or other immunotherapy for CSCC.
What Are the Conditions for Reimbursement?
Libtayo should only be reimbursed for a maximum of 48 weeks, if prescribed by oncologists with expertise in the management of patients with skin cancers, and if the cost of Libtayo is reduced. Important budget impact considerations must be addressed for health systems to be able to adopt Libtayo.
Review Background
Disease background: CSCC is a type of skin cancer occurring most frequently in areas exposed to sunlight. As of 2017, the incidence of keratinocyte carcinoma, which consists of both basal cell carcinoma (80% of cases) and CSCC (20% of cases), was reported as 345 per 100,000 females and 369 per 100,000 males in Ontario.
Indication and reimbursement request: Cemiplimab (Libtayo) has been approved by Health Canada “for the adjuvant treatment of adult patients with CSCC at high risk of recurrence after surgery and radiation.” The sponsor is seeking reimbursement for this patient population.
Drug under review: Cemiplimab is a PD-1 inhibitor. It is available as solution for IV infusion and the dosage recommended in the product monograph is 350 mg every 3 weeks for 12 weeks, followed by 700 mg every 6 weeks or 350 mg every 3 weeks.
Treatment costs: At the submitted price of $8,200.00 per vial, the per 28-day cycle cost of cemiplimab is expected to be $10,933.33 per patient (21-day cycle = $8,200.00), based on the Health Canada–recommended dosage.
Highlights of Input From Interested Parties
The patient groups (Melanoma Canada and Save Your Skin Foundation) noted the following regarding impacts of the disease, unmet needs, and important outcomes:
CSCC is associated with pain, fatigue, and treatment-related scarring or disfigurement, particularly in visible areas, leading to impaired self-image and social withdrawal. Patients also reported a substantial psychological burden, including anxiety, depression, and fear of recurrence, resulting in an overall negative impact on QoL and daily functioning.
Treatment goals include reducing the risks of disease recurrence and disease progression, improving survival, and maintaining or improving QoL. Patients also emphasized the importance of minimizing treatment- or surgery-related side effects (e.g., scarring, pain), preserving physical function and appearance, and maintaining the ability to carry out daily activities and work. Access to effective and less invasive treatment options was identified as a key priority.
The clinician group (Ontario Health [Cancer Care Ontario] Skin Cancer Drug Advisory Committee) and the clinical experts consulted by CDA-AMC noted the following regarding unmet needs arising from the disease and the place in therapy for the drug under review:
There are currently no available adjuvant systemic treatment options for patients with CSCC at high risk of disease recurrence following surgery and radiation. These patients remain at substantial risk for disease recurrence, which is associated with worse survival and reduced QoL.
There is a critical need for treatments that reduce disease recurrence and associated patient and health care system burden.
The participating public drug programs provided input regarding considerations for renewal and prescribing of therapy as well as system and economic considerations.
Recommendation
With a vote of 15 to 0, pERC recommends that cemiplimab be reimbursed for the adjuvant treatment of adult patients with CSCC at high risk of recurrence after surgery and radiation only if the conditions listed in Table 1 are met.
Table 1: Reimbursement Conditions and Reasons
Reimbursement condition | Reason | Implementation guidance |
|---|---|---|
Initiation | ||
1. Treatment with cemiplimab should be reimbursed when initiated in adult patients with high-risk CSCC following surgery and radiotherapy. | Evidence from the C-POST trial demonstrated that treatment with cemiplimab resulted in a clinically meaningful benefit in patients with these characteristics. | pERC noted that the definition of high-risk CSCC varies across guidelines and advised jurisdictions that they should follow the definition of high risk used in the C-POST trial given that the benefit of cemiplimab was observed in patients who met those criteria. In the C-POST trial, high-risk disease was defined as 1 of:
pERC emphasized that patients must have received radiotherapy, unless it was contraindicated. |
2. Patients should have good performance status. | Patients with an ECOG PS score of 0 to 1 were included in the C-POST trial. | pERC agreed with the clinical experts that patients with an ECOG PS score > 1 may be treated at the discretion of the treating clinician. |
3. Patients must not have any of the following characteristics: 3.1. previous solid-organ or stem cell transplant 3.2. concurrent cancer other than localized CSCC 3.3. prior immunotherapy for CSCC 3.4. a history of immune-related pneumonitis or ILD. | Patients with these characteristics were excluded from the C-POST trial. | — |
Discontinuation | ||
4. Treatment with cemiplimab should be discontinued upon the occurrence of any of the following: 4.1. disease recurrence or progression 4.2. unacceptable toxicity 4.3. completion of 48 weeks of treatment. | In the C-POST study, treatment with cemiplimab continued for a maximum of 48 weeks or until disease recurrence or the occurrence of unacceptable toxicity. | pERC and the clinical experts noted that there was no evidence reviewed to support re-treatment with cemiplimab. Furthermore, pERC and the clinical experts consulted by CDA-AMC noted that patients who stop treatment with cemiplimab for reasons other than disease progression or toxicity (e.g., treatment break) may be considered eligible to restart treatment upon disease progression at the discretion of the treating clinician. |
Prescribing | ||
5. Cemiplimab should be prescribed by oncologists with expertise in the management of patients with skin cancers. | This is meant to ensure that cemiplimab is prescribed for appropriate patients and that adverse effects are managed in an optimized and timely manner. | — |
Pricing | ||
6. A reduction in price. | Using the CDA-AMC base-case analysis, the ICER for cemiplimab was $370,253 per QALY gained when compared with routine surveillance in the indicated population. A band 2a price reduction would be required to achieve cost-effectiveness at a $50,000 per QALY gained threshold. A band 2a price reduction would be required to achieve cost-effectiveness at a $100,000 per QALY gained threshold. Exact price reductions at any given willingness-to-pay threshold can be found in the CDA-AMC Main Report and in the Supplemental Material document. | The CDA-AMC analysis is based on public list prices for all treatments. Further price reductions may be required if there are price arrangements (discounts) currently in place for any treatment included in the economic analysis. Likewise, further price reductions may be required to address the economic feasibility of adoption. |
Feasibility of adoption | ||
7. The economic feasibility of adoption of cemiplimab must be addressed. | At the submitted price, the magnitude of uncertainty in the budget impact must be addressed to ensure the feasibility of adoption, given the difference between the sponsor’s estimate and the CDA‑AMC estimate(s). | Further price reductions may be required to address the economic feasibility of adoption if adjuvant treatment is extended to adult patients with high-risk CSCC following surgery for whom radiotherapy is contraindicated. |
CDA-AMC = Canada’s Drug Agency; CSCC = cutaneous squamous cell carcinoma; ECOG = Eastern Cooperative Oncology Group; ICER = incremental cost-effectiveness ratio; ILD = interstitial lung disease; pERC = pan-Canadian Oncology Drug Review Expert Review Committee; PS = performance status; QALY = quality-adjusted life-year.
aFor the statement regarding the size of the price reduction required, band 1 = 1% to 24%, band 2 = 25% to 49%, band 3 = 50% to 74%, and band 4 = 75% or greater.
Rationale for the Recommendation
Clinical Value
Based on the totality of the clinical evidence, pERC concluded that cemiplimab demonstrates acceptable clinical value compared with active surveillance in patients with CSCC. Given that cemiplimab is expected to be an additive treatment to active surveillance, acceptable clinical value refers to added value versus active surveillance.
Evidence from 1 phase III randomized controlled trial (C-POST; N = 415) demonstrated that treatment with cemiplimab for 48 weeks likely results in added clinical benefit compared to active surveillance alone for DFS in patients at high risk for disease recurrence who have had prior surgery and radiation therapy. Although the median DFS was not reached in either treatment group, the results favoured cemiplimab (hazard ratio [HR] = 0.354; 95% confidence interval [CI], 0.229 to 0.548). Landmark analyses for the proportions of patients alive and having disease-free status at 12 and 36 months were consistent with and supportive of the primary end point (93.0% in the cemiplimab group versus 71.5% in the placebo group at 12 months; and 82.3% versus 61.9%, respectively, at 36 months), and pERC and the clinical experts considered the results to be clinically meaningful. pERC highlighted that the median overall survival (OS) was not reached in either group, and Kaplan-Meier estimates of OS demonstrated no difference between cemiplimab and placebo (HR = 0.782; 95% CI, 0.392 to 1.557). As such, pERC considered the results for OS to be uncertain and could not conclude that cemiplimab is associated with improvements in survival. Although there is increased toxicity associated with cemiplimab treatment, pERC and the clinical experts noted that the side effect profile of cemiplimab from the C-POST trial was consistent with that of immunotherapy and was considered manageable.
Patients identified a need for accessible treatments that reduce the risk of disease recurrence, as this often necessitates additional and potentially more burdensome interventions (e.g., repeat surgery, radiation therapy, intensive wound care, and increased hospitalizations). Patients emphasized the importance of therapies that help avoid repeated procedures, minimize treatment- and surgery-related adverse effects, and maintain or improve QoL. pERC concluded that cemiplimab met some patient needs because it is an additional treatment option that reduces the risk of disease recurrence and has manageable side effects. While patients also expressed a need for treatments that maintain QoL, no definitive conclusions could be reached regarding the effects of cemiplimab on health-related QoL (HRQoL).
Further information on the committee’s discussion around clinical value is provided in the Summary of Deliberation section.
Developing the Recommendation
The determination of acceptable clinical value was sufficient for pERC to recommend reimbursement of cemiplimab. As part of the deliberation on whether to recommend reimbursement, the committee also considered unmet clinical need, unmet nonclinical need, and health inequity. Information on this discussion is provided in the Unmet Clinical Need and Distinct Social and Ethical Considerations domains in the Summary of Deliberation section.
Because pERC recommended that cemiplimab be reimbursed, the committee also deliberated on whether reimbursement conditions should be added to address important economic considerations, health system impacts, or social and ethical considerations, or to ensure clinical value is realized. The resulting reimbursement conditions, with accompanying reasons and implementation guidance, are stated in Table 1.
Summary of Deliberation
pERC considered all domains of value of the deliberative framework before developing its recommendation: clinical value, unmet clinical need, distinct social and ethical considerations, economic considerations, and impacts on health systems. For further information on the domains of value, refer to Expert Committee Deliberation at Canada’s Drug Agency.
The committee considered the following key discussion points, organized by the 5 domains of value.
Clinical Value
Appropriate comparators: Beyond surgical resection and radiation therapy, the committee noted that there are no available alternative systemic treatments in the adjuvant setting for patients with high-risk disease. As such, pERC noted that active surveillance was an appropriate comparator for cemiplimab in the patient population being considered.
Efficacy versus active surveillance: One phase III randomized, placebo-controlled study (C-POST) demonstrated that 48 weeks of treatment with IV cemiplimab was associated with statistically significant improvements in DFS compared to placebo, despite the median DFS not being reached in either treatment group (HR = 0.354; 95% CI, 0.229 to 0.548). The probability of DFS at both 12 and 36 months was consistent with the primary analysis (at 12 months: 93.0% versus 71.5%; at 36 months: 82.3% versus 61.9%), in favour of cemiplimab in each case (mean difference in event-free probability at 12 months: ████%; 95% CI, ███ ████████; mean difference in event-free probability at 36 months: ████%; 95% CI, ███ ████████. After 30.1 months of follow-up, the median OS was also not reached in the cemiplimab or placebo group, and there was no difference between groups (HR = 0.782; 95% CI, 0.392 to 1.557). In both groups, HRQoL — measured by the European Organisation for Research and Treatment of Cancer Quality of Life Questionnaire Core 30 Global Health Status score — decreased from baseline in the cemiplimab group (least squares mean change from baseline, −1.95 points; 95% CI, −4.27 points to 1.77 points) and in the placebo group (least squares mean change from baseline, −1.02 points; 95% CI, −3.42 points to 1.39 points), though there was no difference between groups (difference in least squares mean change, −0.94 points; 95% CI, −3.65 points to 1.77 points).
Certainty of the evidence: pERC discussed the Grading of Recommendations Assessment, Development and Evaluation (GRADE) certainty of evidence assessment of the evidence from the C-POST trial. pERC noted that compared to placebo, 48 weeks of treatment with cemiplimab likely resulted in clinically meaningful improvements in DFS, with moderate certainty. In general, the certainty of evidence was rated down due to a small number of events and due to a lack of precision associated with longer follow-up times. Thresholds for clinically meaningful between-group differences were suggested by the clinical experts consulted by CDA-AMC for the probabilities of DFS and OS at 12 months (15% and 2%, respectively) and at 36 months (10% and 5%, respectively). Based on these thresholds, the results for DFS may be considered clinically important for patients with CSCC at high risk of recurrence. pERC discussed DFS as a surrogate end point for OS in patients with CSCC, noting that there are no validation studies available involving participants with CSCC at high risk of recurrence for review; however, the clinical experts consulted by CDA-AMC considered DFS to be a valid outcome for this disease.
Clinical importance of treatment effects: Based on the input from patient and clinician groups, preventing recurrence is a clinically important goal of treatment in this setting given the clinical consequences of recurrence, which may include repeat surgery, additional radiotherapy, and intensive wound care, which can cause scarring, disfigurement, pain, and psychological harm (e.g., anxiety, social withdrawal). The committee acknowledged the clinical relevance of DFS; however, the committee questioned whether cemiplimab reduces many of these potential sequelae. In the C-POST trial, of the patients with disease recurrence (18 [8.6%] who received cemiplimab and 61 [29.6%] who received placebo), ██████ and ██ ███████ received subsequent surgery or radiation. The committee also discussed the clinical importance of tumour location and location of recurrence (i.e., locoregional and/or distant); there were █████ and █████ patients in the cemiplimab group and █████ and █████ patients in the placebo group with locoregional and distant recurrence, respectively. pERC noted that at baseline, 82.7% of patients had primary tumours in the head and neck region; thus, locoregional recurrence in this area may be more disfiguring. The committee considered OS to be a clinically important outcome in patients with CSCC, particularly given the older age of this population and the presence of competing mortality risks. However, the C-POST trial did not demonstrate an OS benefit with adjuvant cemiplimab compared with active surveillance. As cemiplimab is also available in the advanced or metastatic setting, uncertainty remains regarding whether adjuvant treatment improves survival or simply shifts treatment to an earlier stage of disease. In this context, adjuvant cemiplimab may expose all eligible patients to treatment-related burden and toxicity earlier than necessary, including those who may never experience disease recurrence, whereas active surveillance reserves treatment for the subset of patients who experience disease recurrence. Therefore, in the absence of demonstrated survival gains, pERC highlighted some uncertainty in the clinical value of adjuvant cemiplimab with respect to OS, which must be weighed against the competing mortality risks of this population.
Definition of high-risk CSCC: pERC discussed the lack of consensus on what constitutes high-risk disease, which could result in inequities in care across the country. The committee also highlighted the importance of establishing and maintaining clear eligibility criteria to ensure appropriate use of therapy. As such, the committee emphasized the need for a standardized, multidisciplinary definition developed through collaboration among surgeons and medical and radiation oncologists at either the provincial and territorial or national level. In discussing high-risk disease, the committee also referred to the KEYNOTE‑630 trial for pembrolizumab (which was not included in the review of cemiplimab conducted by CDA-AMC) in the same disease space. The KEYNOTE-630 trial did not result in statistically significant improvements in recurrence-free survival, and the committee noted it had different inclusion and exclusion criteria and had used a different definition of high-risk disease compared with the C-POST trial. Given these considerations, the committee considered it appropriate to align with the definition of high-risk disease used in the C-POST trial, as this definition directly reflected the population in which the treatment effect was evaluated.
Other considerations: pERC discussed the lack of evidence for part 2 of the C-POST trial, which allowed re-treatment with cemiplimab for up to 96 weeks after a disease-free interval of 3 months. However, pERC and the clinical experts noted that there was no evidence reviewed to support re-treatment with cemiplimab.
Clinical value: Based on the preceding considerations, the committee determined there was added clinical value of cemiplimab versus active surveillance.
Unmet Clinical Need
Input on unmet clinical need: The committee noted that surgery for CSCC is potentially curative; however, patients emphasized the physical and emotional burdens associated with surgery and highlighted the importance of minimizing treatment or surgery-related side effects (e.g., scarring, pain) and preserving appearance. Additionally, disease recurrence often necessitates additional, more morbid interventions (e.g., repeat surgery, radiation, intensive wound care, and increased hospitalizations). As such, the committee agreed with patients and clinicians that there is a need for treatment options that reduce the risk of disease recurrence, particularly in patients at high risk for recurrence, and prevent repeated interventions.
Severity of the disease: Despite treatment with surgery and radiotherapy, patients with high-risk CSCC remain at substantial risk for disease recurrence, metastasis, and death. The 2-year DFS rate for patients with high-risk features is 64%. The patient group input emphasized fear of disease recurrence. pERC noted that recurrences — particularly in the head and neck — often require repeated, disfiguring surgery and additional radiation therapy, which may cause functional impairment and loss of QoL.
Availability of treatment options: pERC noted there are currently no approved and/or funded adjuvant therapies in Canada for patients with high-risk CSCC following surgery or radiation.
Distinct Social and Ethical Considerations
Input on unmet nonclinical need: pERC acknowledged the nonclinical needs that patients with CSCC may experience, such that minimizing the number of recurrences may decrease the burden on patients, caregivers, and health care systems. However, the committee noted that cemiplimab does not address nonclinical needs given the need for IV administration over 48 weeks and the associated laboratory tests and physician visits required, as well as potential toxicity.
Equity considerations: The committee acknowledged that definitions of high-risk disease vary (e.g., versions used by the National Comprehensive Cancer Network [in the US], Brigham and Women’s Hospital, and the American Joint Committee on Cancer, as well as that used in the C-POST trial), and they vary by jurisdiction. This means that patients whose disease is considered to have a high risk for recurrence and who are eligible for treatment in 1 jurisdiction may not meet the criteria for treatment in another. pERC noted that this variability may create inequities in access to therapy, leading to differences in treatment opportunities and outcomes for patients with similar disease characteristics. pERC also remarked that cemiplimab is an IV treatment that does not address access barriers for patients living in remote areas in which travel may be required to receive care, which could introduce additional barriers and burdens (e.g., travel and related expenses) for patients and caregivers.
Economic Considerations
Health impacts of cemiplimab versus relevant comparators: When compared to routine surveillance, cemiplimab is not predicted to be associated with a gain in life-years (LYs) but may result in a gain of 0.17 quality-adjusted LYs (QALYs) due to QoL improvement over a lifetime (30-year) horizon.
Cost of cemiplimab versus relevant comparators: Cemiplimab is predicted to be associated with higher costs to the health care system than routine surveillance (incremental costs = $62,759) over a lifetime (30-year) horizon, primarily driven by increased costs associated with drug acquisition. Adjuvant cemiplimab is predicted to be associated with an additional $117,638 per patient in drug costs in the first line.
Key findings of the economic evaluation: Based on the submitted evidence using the sponsor’s cost-utility analysis, the CDA-AMC base-case analysis estimated that the incremental cost-effectiveness ratio (ICER) for cemiplimab in patients with CSCC at high risk of recurrence was $370,253 per QALY gained when compared with routine surveillance (Figure 1). Of the incremental benefit compared to routine surveillance (0.17 incremental QALYs), approximately 77% of the benefit was predicted to be accrued after the observation period of the C-POST trial. However, the modelling approach assumed an HRQoL benefit associated with remaining in the recurrence-free state, which is not supported by the trial evidence. As a result, the results of the CDA‑AMC base case may have overestimated QALY gains associated with cemiplimab.
Figure 1: Estimate of the ICER Used by pERC to Inform the Price Condition
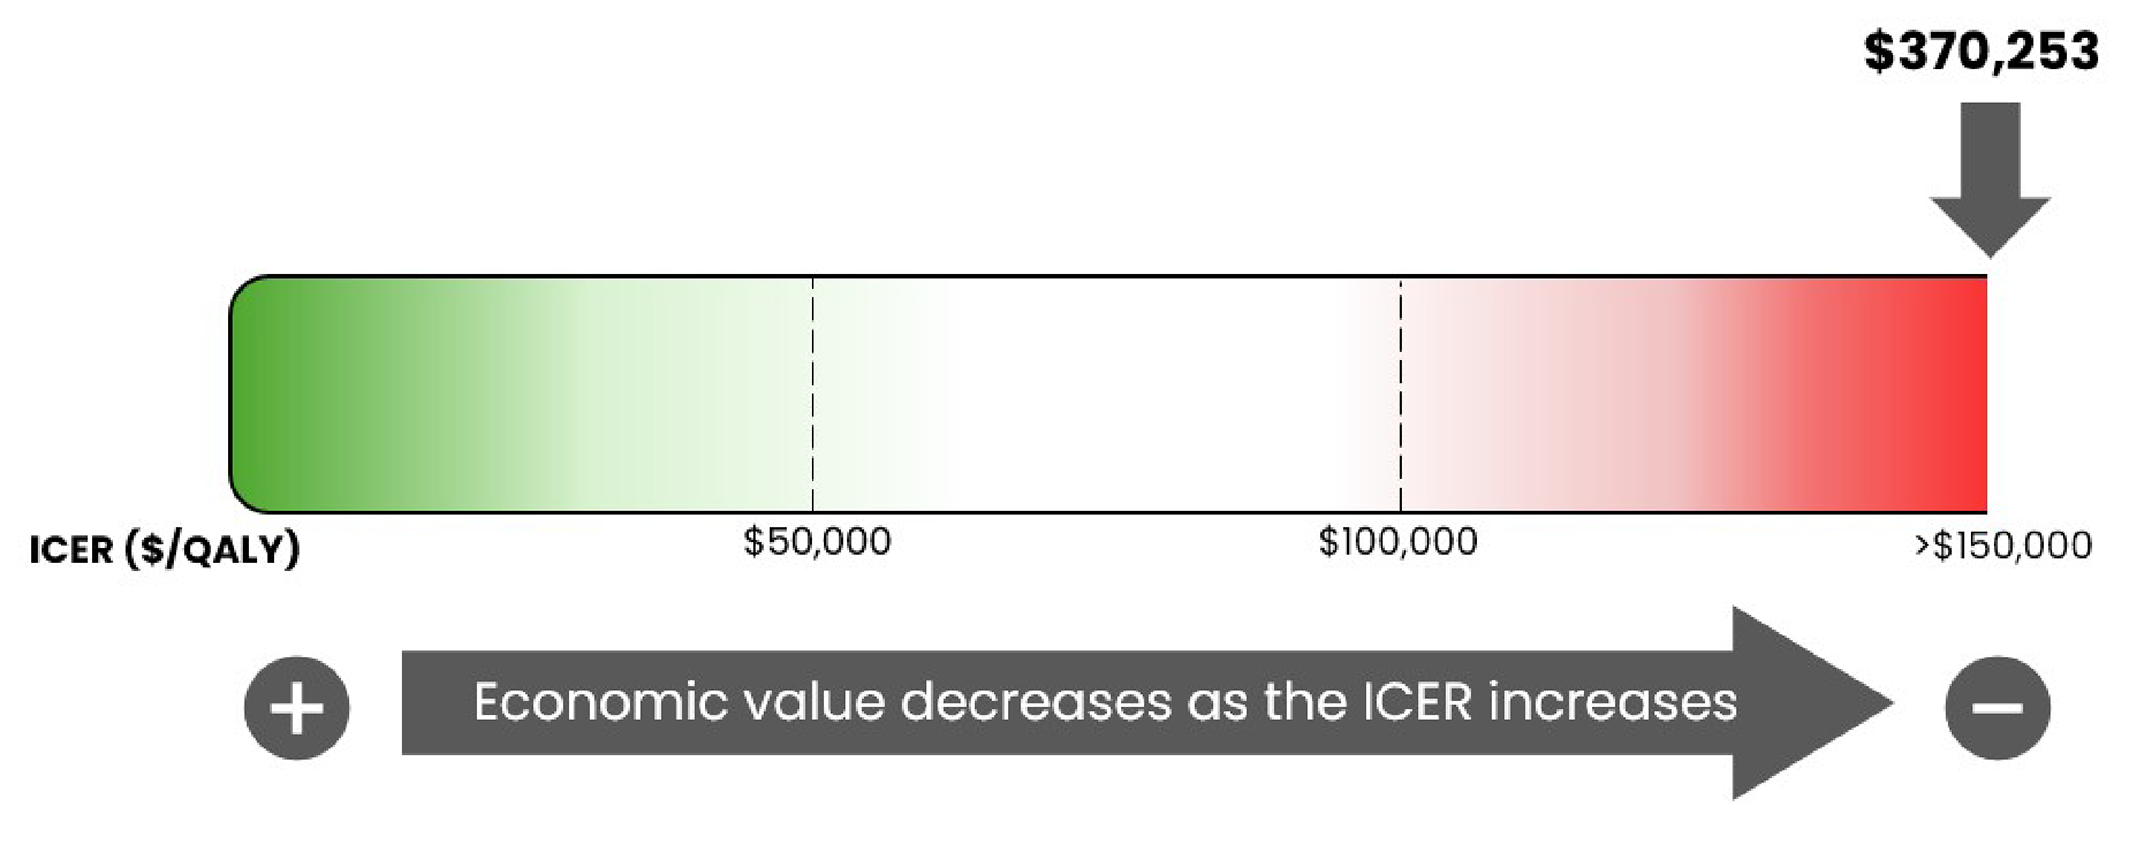
ICER = incremental cost-effectiveness ratio; pERC = pan-Canadian Oncology Drug Review Expert Review Committee; QALY = quality-adjusted life-year.
Certainty of the evidence: The estimated cost-effectiveness of cemiplimab compared to routine surveillance was informed by post hoc analyses of the C-POST trial that could not be validated by CDA-AMC, especially concerning OS benefits produced from these data, which were inconsistent with the prespecified OS analysis results. This introduced a high risk of bias and high imprecision in the results, resulting in QoL benefits that were not supported by the trial data.
Other considerations: pERC agreed with the clinical experts that adult patients with high-risk CSCC following surgery, for whom radiotherapy is strictly contraindicated, may be candidates for treatment with cemiplimab. As this subgroup was not represented in the clinical trial and was not considered in the economic model, the clinical benefits and cost-effectiveness of cemiplimab in this population are unknown. Therefore, further price reductions may be required to ensure cost-effectiveness of adjuvant treatment with cemiplimab and to address the economic feasibility of adoption.
Impacts on Health Systems
Anticipated budget impact: In the CDA-AMC base case, the 3-year budget impact of reimbursing cemiplimab for CSCC was $25,544,668 (year 1 = $6,669,736; year 2 = $7,826,208; year 3 = $11,048,724), with an estimated expenditure of $25,544,668 on cemiplimab over this period. CDA-AMC estimated that 421 patients would be eligible for cemiplimab over a 3-year period (year 1 = 137; year 2 = 140; year 3 = 144), of whom 183 would be expected to receive cemiplimab (year 1 = 48; year 2 = 56; year 3 = 79). The actual budget impact of reimbursing cemiplimab will depend on the number of patients eligible for treatment, its uptake, and the impact on the costs associated with subsequent therapy (which is not reflected in the budget impact analysis). The sponsor did not include the cost of subsequent treatment in the budget impact analysis, and the budget impact in the CDA-AMC base case may therefore have been overestimated; however, the magnitude of this potential overestimation could not be quantified.
Other considerations: pERC noted that the actual budget impact of adopting adjuvant treatment with cemiplimab may be underestimated if adult patients with high-risk CSCC following surgery, for whom radiotherapy is strictly contraindicated, are eligible for treatment with cemiplimab. A scenario analysis in which all adult patients with high-risk CSCC following surgery are considered eligible for treatment resulted in the 3-year budget impact being $85,148,892 (year 1 = $22,232,453; year 2 = $26,087,358; year 3 = $36,829,081). pERC acknowledges that this may have overestimated the actual budget impact associated with cemiplimab as not all adult patients with high-risk CSCC following surgery may want to pursue adjuvant treatment due to its side effects. However, the analysis was intended to explore the upper bound of plausible budget impact. Additionally, pERC noted that adjuvant treatment with cemiplimab may place further strain on oncology capacity, as patients who would otherwise undergo routine postsurgical surveillance would require ongoing assessment and management by oncologists for adjuvant treatment. Therefore, further price reductions may be required to address the economic feasibility of adoption of adjuvant treatment with cemiplimab.
Sources of Information Used by the Committee
To make its recommendation, the committee considered the following information (links to the full documents for the review can be found on the project web page):
the CDA-AMC review of the clinical and pharmacoeconomic evidence submitted by the sponsor, as well as relevant ethical issues related to cemiplimab (refer to the Main Report and the Supplemental Material document)
the sponsor’s comments on the draft report and the CDA-AMC responses
patients' perspectives gathered by 2 patient groups, Melanoma Canada and Save Your Skin Foundation (refer to the Patient and Clinician Group Input document)
input from 1 clinician group, Ontario Health (Cancer Care Ontario) Skin Cancer Drug Advisory Committee (refer to the Patient and Clinician Group Input document)
input from public drug programs that participate in the reimbursement review process (refer to the Supplemental Material document)
input from 2 clinical experts with expertise in the management of CSCC consulted by CDA-AMC.
pERC Information
Members of the Committee
Dr. Catherine Moltzan (Chair), Dr. Kelvin Chan (Vice-Chair), Paul Agbulu, Dr. Phillip Blanchette, Dr. Matthew Cheung, Annette Cyr, Dr. Jennifer Fishman, Dr. Prafull Ghatage, Dr. Jason Hart, Terry Hawrysh, Dr. Yoo-Joung Ko, Dr. Aly-Khan Lalani, Amy Peasgood, Dr. Anca Prica, Dr. Michael Raphael, Dr. Adam Raymakers, Dr. Patricia Tang, Dr. Pierre Villeneuve, and Danica Wasney.
Meeting date: August 12, 2026
Regrets: Three expert committee members did not attend.
Conflicts of interest: None
ISSN: 2563-6596
Canada’s Drug Agency (CDA-AMC) is a pan-Canadian health organization. Created and funded by Canada’s federal, provincial, and territorial governments, we’re responsible for driving better coordination, alignment, and public value within Canada’s drug and health technology landscape. We provide Canada’s health system leaders with independent evidence and advice so they can make informed drug, health technology, and health system decisions, and we collaborate with national and international partners to enhance our collective impact.
Disclaimer: CDA-AMC has taken care to ensure that the information in this document was accurate, complete, and up to date when it was published, but does not make any guarantee to that effect. Your use of this information is subject to this disclaimer and the Terms of Use at cda-amc.ca.
The information in this document is made available for informational and educational purposes only and should not be used as a substitute for professional medical advice, the application of clinical judgment in respect of the care of a particular patient, or other professional judgments in any decision-making process. You assume full responsibility for the use of the information and rely on it at your own risk.
CDA-AMC does not endorse any information, drugs, therapies, treatments, products, processes, or services. The views and opinions of third parties published in this document do not necessarily reflect those of CDA-AMC. The copyright and other intellectual property rights in this document are owned by the Canadian Agency for Drugs and Technologies in Health (operating as CDA-AMC) and its licensors.
Questions or requests for information about this report can be directed to Requests@CDA-AMC.ca.